Categories

Category: Health Tech

Value Is in the Eye of the Beholder

By KIM BELLARD

The most (unintentionally) amusing story I read this week was Tim Higgin’s Wall Street Journal article Alex Karp Is Saying What Every Angry CEO Is Thinking About AI. Dr. Karp (yes, he has a Ph.D.), co-founder and CEO of Palantir Technologies, is upset about how AI companies are using relationships with their business customers to harvest data and business insights from those customers. “Something has gone completely wrong,” he fumed.

Now, this is Palantir, mind you; it may not have invented surveillance capitalism but it might have perfected it. It has become essential to government and large corporations across the world. Most of us are aware of how tech companies like Meta or Google give us “free” services that exist primarily to collect more data on us, which they then use to target ads to us, but Palantir’s data collection and analysis operate at a level we often don’t recognize.  But make no mistake; it is using our data, and not necessarily in our best interests.

Mr. Higgins quotes former White House AI czar David Sacks in support of Dr. Karp’s concerns:

Anthropic has launched Claude Science, Claude Security, Claude Legal, and of course Claude Code—each expanding into categories previously served by companies building on top of their models. The pattern is consistent: Watch where value is being created, then move in directly. Dominate the model layer, then use that position to capture the most lucrative verticals.

So it is delicious irony that Dr. Karp and others are finding themselves at the wrong end of the power inequality with their data.

I find myself thinking about healthcare when I think above this new wave of data collectors/ synthesizers. It seems pretty clear that the AI companies aren’t going anywhere, and are expected to reshape most industries, including healthcare. Lots has been written about AI’s use in healthcare, including by me. It is both inevitable and, in many cases, desirable. Now this issue of AI’s insatiable appetite for data makes me wonder if we’re looking at things wrong.

I’ve worked in healthcare for longer than I care to admit, and at no point did people not complain that healthcare in general, and health insurance in particular, was too expensive. And yet, costs have kept rising. We’re closing in on $6 trillion in U.S. healthcare expenditures. No matter what kind of health insurance you have – large employer, small employer, ACA Marketplace, Medicare Advantage, even Medicare Supplements for traditional Medicare – your premiums (and/or out-of-pocket costs) are likely going up at rates we haven’t seen in years.

Two well known facts about rising costs are, one, that it is not so much we’re using too many services as it is that Americans pay way higher prices for healthcare than in most countries, and, two, that a relatively small percentage of people account for the vast majority of healthcare spending. The latter has an insidious effect on health insurance premiums, as people with fewer expenses are less likely to have or keep health insurance, making premiums for the remaining people higher. Nobody wants to pay for the people who use a lot of health care, but they want other people to help pay if they end up being one of those people. It’s a conundrum.

Now, optimists hope that AI can do a better job of identifying all the wasted, unnecessary, or inappropriate care we use – estimated as much as one-third – and help make administration more efficient; current levels are estimated as 15-30% of spending. Good goals, both of them, and it is entirely plausible that AI can help with both. But it would still remain that sick people are the “problem” with our health care spending and health insurance premiums, and I want to propose a different way of looking at them.

Continue reading…


The wrong people are scared of clinical AI

By CRAIG HAUBEN

Ask anyone outside healthcare who resists clinical AI and you’ll get a confident answer. The older doctors. The ones who spent thirty years building expertise and now see a machine coming for it. The story writes itself, which should have been the first clue it was wrong.

I’ve spent thirty years in healthcare, and I now run a company that builds and runs AI inside provider and payer organizations. At Clutch we use AI’s data analysis to solve engagement challenges. Who is the patient today? What message will land with them? When do they want to read it? Get those right and you can drive the kind of sustained behavior change that moves clinical outcomes like drug adherence, care plan adherence, and gap closure.

So I’m not working from theory. I watch this land in real workflows, and here’s what I see. The clinicians most enthusiastic about AI are usually the ones who’ve done the job the longest. The resistance comes from somewhere else. If you run a health system, that difference should change how you plan your next deployment.

Start with the adoption numbers, because they already break the resistance story. The AMA’s latest survey found four in five physicians now use AI in practice, up from 38 percent in 2023. That’s not a profession digging in against a threat. That’s a profession that found something useful.

Now the veterans. A doctor with three decades in a specialty can see, better than anyone, what these systems are good at. Pattern recognition at scale. Catching the thing that should have been flagged two visits ago. Surfacing what was already sitting in the data: the missed finding in last year’s imaging, the lab trend across eighteen months that looked unremarkable one value at a time, the three ED visits in six weeks nobody had the time to connect.

This isn’t hypothetical. The Nature study of Google’s breast cancer screening system showed a 9.4 percent drop in false negatives for US patients, the cancers human readers missed. The largest NHS evaluation to date, across 175,000 women, found AI caught more invasive cancers with fewer false positives than human readers. The harm these systems go after, information that existed and never got connected, is one experienced clinicians know cold. They’ve spent careers watching its absence hurt people.

Here’s one from our own work. We’re working with a national government programs payer on some of their hardest members to engage, the high intensity ones who need contact four or five times a day for six months or more. We got engagement to 95 percent, measured by the customer, and adherence to 93 percent. The result was a 0.8 average drop in HbA1c and an 18 percent reduction in symptoms.

When a system takes the mechanical load off so the judgment work gets more attention, the thirty-year clinician doesn’t feel threatened. They feel relieved. Their expertise is the judgment, not the data retrieval, and they’ve always known the difference.

Now look at where the fear actually lives. It comes from the middle.

Continue reading…

Future of AI and Telehealth in primary care — Panel discussion

A couple of months back I hosted a conversation about my favorite topics, primary care and how telehealth and AI are changing it. The panel was Timm Schneider — Co-Founder & COO, Third Way Health, Jamie Reddick — COO, Graybill Medical Group & Erin Parks, Ph.D. — Co-Founder, Equip. The panel was at a tech heavy conference called TechCon Global in San Diego. Sadly the weather stopped us getting Matt Siegler from Akido Labs. We got into it about tech. incentives, specialty care and the role of AI in access and patient support–Matthew Holt

How Online Prescription Services Are Closing the Access Gap for Patients Who Skip the Doctor’s Office

By DAMIAN WONJO

Every clinician keeps a private list of the patients they don’t see. Not the ones who cancel, the ones who never book. The shift worker who reschedules the same appointment three times and then quietly gives up. The parent who can’t justify half a day off and a waiting-room afternoon for a routine refill. The patient whose condition carries enough stigma that the friction of a face-to-face visit becomes, in itself, a reason to do nothing. These people don’t show up in no-show statistics. They show up later, as complications, as emergencies, as avoidable deterioration.

This is the access gap, and from where I sit as a physician in Europe, it has less to do with the raw supply of doctors than with the cost of reaching one, measured not only in money but in time, distance, and effort. When that cost climbs higher than a patient’s tolerance, care simply doesn’t happen. Online prescription services and remote consultation won’t fix every part of this problem. But they target precisely the variable that most reforms ignore, which is friction.

The patients who fall through

It is tempting to frame telemedicine as a convenience for the already-healthy and already-connected. In practice, the people who benefit most are often those with the least slack in their lives. A patient stabilised on the same antihypertensive for three years does not need a fresh diagnostic odyssey to continue it, they need a prescription before they run out. A working adult who recognises a recurring, familiar problem does not always need a physical examination to be helped safely. Forcing every such encounter through the narrow door of an in-person appointment does not raise the standard of care, it raises the rate at which people abandon it.

Continuity is where this matters most. Chronic conditions are managed in refills, and a missed refill is not a clerical event but a gap in treatment with real physiological consequences. Lowering the barrier to that refill is not a luxury. It is, quietly, one of the highest-yield interventions available.

What changed in Europe

The pandemic did not invent telemedicine, but it normalised it, and it accelerated the infrastructure underneath it. Poland is a useful case study. Electronic prescriptions became the national standard in 2020, and today essentially every prescription is issued digitally, retrievable by the patient through a government health account and dispensable at any pharmacy with a code. The clinical encounter and the prescription were decoupled from a single physical location without being decoupled from a licensed prescriber.

That distinction is the whole argument. A responsible online prescription service is not a vending machine. It is a licensed physician, working within the same legal and ethical framework as any clinic, using a different channel to reach the patient. The technology is mundane. The consequence, that a patient who would otherwise have gone without is now seen, is not.

Continue reading…

A ridiculously stupid letter from a health insurer

By MATTHEW HOLT

It’s hard to imagine but I may now be in possession of the stupidest letter I’ve ever received from an American health insurance company–-and I’m the guy who got five identical letters on one day from Blue Shield of California telling me that they had changed my primary care doctor when I had initiated the change.

A little backstory.  As those you’ve been following along with my various telenovelas may remember that last year I was diagnosed with a failing heart valve.  I also have a failing left knee due mostly to snowboarding into a tree 24 years ago.

I was attempting to put off doing anything about the heart valve for as long as possible because it sounds painful and unpleasant, and I was hoping that I could go ahead with a knee replacement so that my snowboarding can continue apace. My doctors are at UC San Francisco and they agreed that I should have the knee replacement on July 6th, assuming that my heart valve had not got much worse. On June 16th I went into UCSF for a bunch of knee replacement pre-workup and they also checked my heart.

However, my new insurance company, thanks to my wife’s new job, is Cigna. Those of you in California may know that Cigna was having a big dispute with the University of California Health system and that its contract with them was due to expire on June the 30th of this year. Why a health plan and a big provider organization have contracts that expire in the middle of the year when the employers and people who use the health plan network buy them on an annual basis starting in January I don’t know –  and it’s ridiculously stupid. But let’s not get distracted cause I’m not talking about that here!

Because of the fact that they’d be out of network, the ortho team made the obvious suggestion that I move the knee replacement a little earlier, In fact it was planned for June the 22nd. This did not upset me too much as you may have seen that some corrupt Italians have organized a soccer tournament that would give me plenty of games on TV to be entertained by while I was lying around recovering.

Sadly one of the pretests I had on June 16th was an echocardiogram that indicated that my heart valve was in even worse shape than it had been earlier in the year.  After quite a lot of back and forth between the cardiac team, the knee team and the anesthesia team, everyone agreed to put off the knee surgery until we figured out my heart.

Meanwhile sometime late on Thursday the 25th or early on Friday the 26th of June, UC Health and Cigna stepped back from the brink and came to an agreement that will continue the UC system being in Cigna’s network.

Which all brings me to July 6th when I received a letter from Cigna

This is the one that contains more stupidity per square inch than any other communication I’ve had from an insurance company.

Continue reading…

Life Not As We Know It

By KIM BELLARD

Well, let’s see. Last week much of the U.S. and parts of Europe were under a crippling heat dome. The U.S. celebrated its 250th birthday. And there’s something called the World Cup going on, for those of you who care about such things. But, I mean, really, the news of the week? SpudCell.

OK, maybe you missed that one. If you are not a fan of science, or of synthetic biology in particular, news about it might not have shown up in your feeds, or perhaps you thought it was another ploy by the Potato Association of America to get you to buy even more potatoes. SpudCell is something truly new: “the world’s first synthetic cell with a complete life cycle, built entirely from non-living chemical components.”

Take a minute to take that description in.

“SpudCell performs the behaviors often used to tell the living from the inert — it feeds, grows, replicates its genome, divides and undergoes selection — yet it is far simpler than any natural cell and was assembled, part by part, by hand,” the project researchers wrote in a statement.

It was designed and built by researchers at the University of Minnesota, announced last week along with a preprint of their paper.The team was led by Professor Kate Adamala, and the name is either due to its supposed resemblance to a potato or it’s a play on “Sputnik.”

“This is likely the most exciting project I’ve ever worked on,” said Professor Adamala. “We’ve replicated in chemistry what only used to be possible in biology: the complete set of behaviors of a cell. It proves that the most fundamental functions of life, like growth and replication, do not need a mysterious magical spark.”

Scientists have been working for decades on stripping away genetic material from living cells to try to find the minimum necessary for life, but Professor Adamala and her team went the other way, gradually building up genetic material until it started behaving in ways we’d expect cells to.

The impressive thing is that the team engineered everything SpudCell does. As The Economist put it: “Everything the resulting cells do, they do because of molecules that Dr Adamala’s team put there. That leaves no room for mysteries.” That’s not true when researchers start with living cells.

Drew Endy, a synthetic biologist at Stanford University, told Carl Zimmer of The New York Times, “It’s a cell that was built, not born. It’s constructed, but it does what cells do.”

SpudCell is very basic.

Continue reading…

THCB Spotlight: Warris Bokhari, Claimable

One of the most interesting follows on Linkedin is Warris Bokhari from Claimable. He’s a British MD, who has had stints not only as a doc in the UK, but also as a health tech and health insurance exec in the US. But now he’s at war with the system, in particular working for patients to overturn denials from insurers using AI. But what exactly is the big picture aim, and how does Warris think that he’s going to fix American health care? We had quite the discussion and we sort of agree, but also don’t. Great discussion and transcript is below the video–Matthew Holt

This was such a great discussion I wanted to publish the transcript. The way I do that is to copy the Youtube generated transcript and drop it into Claude to smooth it over. I then read it and if I think it’s made an error, dip back into the video and listen to what actually happened and make a correction. This is all code therefore for me saying I think this transcript is pretty accurate but it might have a bunch of AI and human generated mistakes.

THCB Spotlight: Warris Bokhari, CEO of Claimable

Continue reading…

The ‌Missing ‌Vital ‌Sign: Why Modern Medicine Still Won’t Measure Sleep

By COLIN LAWLOR

A patient comes in for an ordinary primary care appointment. The nurse runs through the usual checklist: temperature, blood pressure, pulse, weight, sometimes pulse oximetry. Sleep probably won’t come up. If it does, it will be a side note, and if the patient says, “not great,” what often follows is a brief look of sympathy and the familiar advice to relax a bit before bed.

That is, more or less, what sleep looks like in the most common diagnostic interaction in American medicine. Don’t worry, it is not much, if any better in any other country. The other vitals get numbers, while sleep gets small talk. Calling this a minor gap misses the point.

What the Evidence Says

Sleep sits among the strongest behavioral and physiological predictors we have for chronic illness, cognitive decline, mental health outcomes, and burnout.

Work out of Stanford recently showed that just one night of sleep data (admittedly from a hospital sleep lab), processed by a foundation model called SleepFM, could flag elevated risk across 130 disease categories with high accuracy. The outcomes on that list are not trivial and include all-cause mortality, dementia, myocardial infarction, and heart failure.

A 2025 umbrella review that pooled 29 systematic reviews found two-way, physiologically mediated links between sleep and depression, anxiety, plus a long catalog of cardiometabolic conditions.

And researchers at Washington State University published what is, so far, the longest objective description of sleep in chronic insomnia. Eight weeks of continuous, in-home measurement pointed to something clinicians have struggled to capture for years: night-to-night swings in sleep efficiency, sleep latency, and intermittent wakefulness are central to the condition. Sleep diaries and one-night lab studies kept missing that pattern.

The clinical rationale for measuring sleep is settled, but what remains unclear is whether medicine intends to behave as if it believes its own evidence.

Continue reading…

Ellipsis Health

Ellipsis Health has come a long way from its roots in detecting depression via vocal biomarkers. Sage, its charming voice AI agent, is now helping health plans and care management companies directly interact with patients and members, helping them with medication reminders, program recruitment, postop follow up and much more. I spoke with two of the brains behind Sage, COO Melissa McCool and CMO Mike Aratow. We got into what she does, what she’s good at and whether the world (or at least the health care world) needs specific voice AI specialists–Matthew Holt

Schrodinger’s Co-pay

By MATTHEW HOLT

More tales of the woes of dealing with health insurance. I live in Marin County, California and one of the things that comes with that is a diagnosis of ADHD for my children. (OK, I have made that joke before but it is true!). My kids now visit a psychiatrist for more sophisticated med management than they receive at their pediatrician. We were (until recently) on a Blue Shield HMO via the Covered California exchange. 

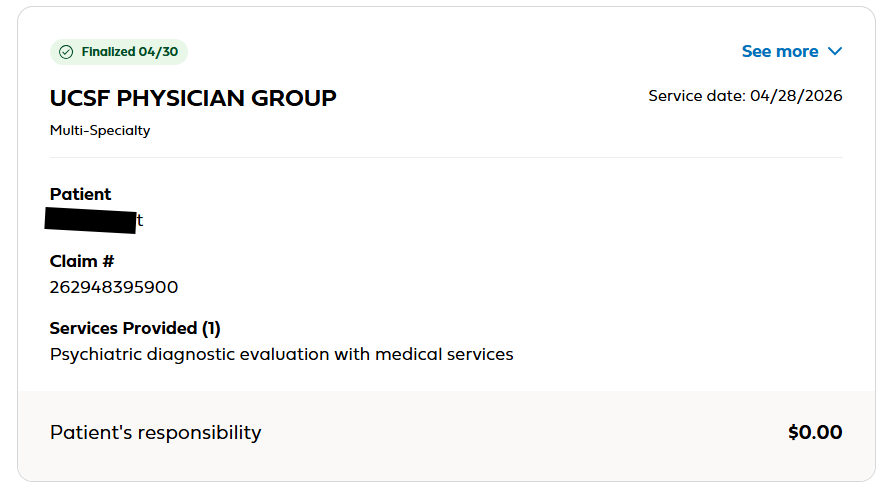
While I was at the doctor’s office, I talked to the staff. They told me I owed a $50 copay. I didn’t pay them (yet) and I went online and saw the claim

The reasonable, informed consumer might think that I owed nothing. The clue being that
“Patient Responsibility” was $0.

But if you click the “See More” in the top right it shows you this

You probably still think that I owe $0. But if you add the numbers on the right you might notice they don’t total $0.

Continue reading…