
Categories

Category: Health Tech

Pre-Surgical Complications (Part 2)

By MATTHEW HOLT

Strap in for the tale of why your hero is spending most of his life down YouTube rabbit holes of cardiology videos while blundering his way around many many medical centers and exposing many problems with American health care even before he gets close to the operating table. Yes it’s Matthew Holt’s pre-surgical complications – the complications that have arisen before he even gets his failing aortic valve fixed. And yes this is a multi-parter! Part 1 here

So on the Friday afternoon I was readying for my video call when there was a car parking emergency. I had to move two Sprinter vans and a car belonging to guests who were all out apres skiing out of our driveway so my wife could get her car out of the garage to get to an appointment she had. Although I was as quick as I could, I was about 10 minutes late for Dr Beygui but he very nicely called me up wondering if I was still okay to do it, was very cordial even though I made him wait, and we had a nice chat. He basically didn’t give me any new information in this conversation and yes UCSF did get paid for it! He was mostly assuming that I couldn’t walk a couple of blocks without getting short of breath but at the end of it we agreed that because I was in good physical shape and able to go snowboarding all day I would go ahead with a knee surgery later in the summer and only come back to him when I became symptomatic. 

Starting in March I got the requisite knee imaging (I had an MRI and 2 X-rays confirming my meniscus is gone and knee was pretty trashed), met with Dr Bini and the ortho team and started prepping for the surgery later that summer–which basically meant going to the gym and doing lots of weights and resistance training on my knees.

A little later I got an unexpected call from Dr Beygui’s physician assistant who told me that he was still trying to line me up for the open heart surgery. I told him I was still keener on a TAVR. He said that I shouldn’t have a TAVR because the TAVR valves only last 5 to 7 years. Yeung from Stanford’s original report told me they lasted about 10 to 12 years. Elmariah the UCSF cardiologist said that they thought they lasted 10 plus years but there was no good data. Given you can probably have one TAVR and then have another put inside when the first one fails and then maybe even another (TAVR in TAVR in TAVR), these numbers actually matter! 

Here’s the crux of the TAVR issue. If you can add 10 + 10 + 10 that gives you another 30 years of life which sounds pretty good to somebody in their early 60s. But if you can’t get more than 5 to 7 years out of a TAVR and can only do one more “TAVR in TAVR”, then you’re getting 10 to 15 years before you need to have a very complicated open heart surgery because it’s now replacing two different artificial valves. In that case I might not survive and I wouldn’t even be old enough to be President!

As you can see this decision is starting to get a little bit complicated. 

But the good news was that I could stop thinking about it because my heart wasn’t getting worse and the orthopedics (and anesthesia) team at UCSF was happy to do the knee replacement. 

As we were all steaming down this path I got a call from Dr Beygui’s scheduling assistant. My initial agreement had been to have an echocardiogram 6 months after the last one which would actually have been after the knee surgery. I’m not sure how much coordination between the departments there was given what happened a bit later but Dr Beygui requested that I have an echocardiogram before any surgery. As I was going in anyway to have a CT in mid-June to prep for the knee surgery, I said fine.

In another great drama of American health care it turns out that my insurance had changed. For most of the first half of the year I purchased a Blue Shield of California HMO on the ACA exchange called Covered California. In May my wife got a job and we then moved over to being covered by her employer’s insurer (well, ASO TPA as it turns out) Cigna.

Cigna and the entire University of California Health system decided to have a dispute which threatened that Cigna would not cover UCSF starting on July 1st. I won’t go into the crazy logic of why an insurance plan that one buys on an annual basis starting in January has contracts with providers that expire in the middle of the year, but welcome to America. Because of this the orthopedic team moved my surgery date up into late June just 4 days after all the prep imaging including that echocardiogram.

Oh and a few weeks earlier I had had a very minor snowboarding fall going very slowly in soft slushy snow. I banged my shoulder but for some reason it didn’t get any better. I actually went and had some physical therapy which seemed to help, but as I was hanging out so much at UCSF, I also had an appointment with the shoulder specialists. They sent me for a pretty uncomfortable MRI and the result from that was that I had total tears in all my rotator cuff tendons. The recommendation for that is surgery that also has a long recovery, but if you ignore it for too long the muscles can atrophy. Claude was very depressed for me when it interpreted that MRI report!

A spanner in the works

Those of you familiar with sod’s law can guess what happens next. The result of the echocardiogram was that the aortic stenosis had gone from being severe to being very severe. The precise number was that my peak velocity went from 4.6 m/s in Jan to  5.1 m/s in June  just 4 and ½ months later.

I discussed this with my trusted health confidant and Claude guessed that this might be a problem and the anesthesia team might not want to have me get the knee surgery.

The next sequence of events reveals that nobody in American healthcare talks to each other.

Continue reading…

Pre-Surgical Complications (Part 1)

By MATTHEW HOLT

Strap in for the tale of why your hero is spending most of his life down YouTube rabbit holes of cardiology videos while blundering his way around many many medical centers and exposing many problems with American health care even before he gets close to the operating table. Yes it’s Matthew Holt’s pre-surgical complications – the complications that have arisen before he even gets his failing aortic valve fixed. And yes this will be a multi-parter!

Introduction and a decent bit of context

Last summer after a lot of back and forth I discovered that I had aortic stenosis. (I won’t replay the whole story of how the referral to the echocardiogram didn’t happen three times and therefore I nearly didn’t have the test and therefore never found out because I already have elsewhere) 

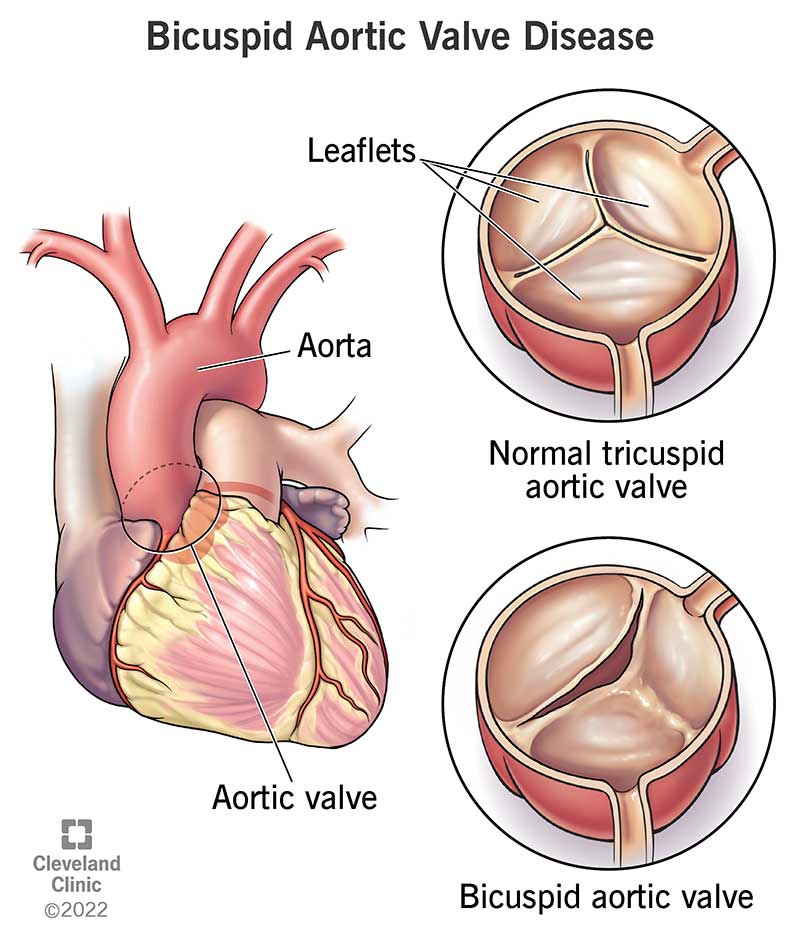
Amazingly this has nothing to do with my bad lifestyle. It’s an inherited heart disease in which the valve that governs the flow of blood between the two main chambers of your heart is starting to fail. Often that means people get very short of breath, start to faint or have severe chest pains but in my case I had none of that. What I did have was the measurement on an echocardiogram showing that my aortic stenosis was “severe” because I have what’s called a bicuspid aortic valve. This is a genetic defect that my father landed me with–well I’m blaming my father but who exactly knows as he’s dead!  

Essentially instead of having three leaves on the valve (like a Mercedes symbol) I have two and over time they’ve been steadily picking up more calcification and opening less. That means that more and more pressure is required from the heart to squeeze blood between the two chambers which is bad for the heart and by extension bad for me. That’s pretty strong agreement amongst cardiologists that if you can get this condition fixed before you become symptomatic it’s better than waiting. If you get symptomatic, it’s urgent and your chance of a heart attack and death becomes pretty high (like 25-50% a year!)

But of course it’s not that simple – either from the standpoint of getting it fixed or from the standpoint of how to get it fixed within the American health care system in all of its beauty. And you can expect it, as it’s me, to hear a lot about customer service, insurance, online access to information and of course interoperability. There might also be some AI thrown in for good measure!

Continue reading…

A digital health company became an insurance carrier under the thin veil of a product launch

By DEEKSHA HEGDE

How to spot a fundamental business model shift from a mile away, long before the PR calls it a product launch or market expansion.

In April 2026, Progyny, a fertility and family building benefits administrator, announced Progyny Select, a supplemental health plan for small and mid-size employers (100-1,000 employees). “Pooled-risk” got me curious: did they cut a deal with an insurance carrier to back the product, or had they taken on insurance risk themselves?

Until now, Progyny had only served large, self-insured employers (1,000+ employees) as a third-party administrator. They negotiated rates with fertility clinics, routed employees to better providers, managed the claims paperwork, and took a margin while employers paid the medical bills. This product launch appeared to be a downmarket expansion to capture a segment previously untapped, but the mechanics were not apparent.

I didn’t have to look very far. It was right there in the legal disclaimer at the bottom of the press release: “through subsidiaries of Progyny Inc. with state licensure to offer supplemental coverage.” Now this really got my attention. This is a digital health company turning into an insurer. You don’t see that happen every day. I decided to do some digging.

What states have they acquired licenses in, given you need one in every state you want to operate in? Their latest 10-K, surprisingly, didn’t mention anything about their flip to the insurer model. I realized they were not required to disclose the new insurance subsidiary since it hadn’t crossed revenue thresholds by the SEC’s definition. The fully insured expansion appeared as a growth target and a regulatory risk factor. They declared the move would subject them to additional laws applicable to health insurance that do not currently apply to them.

The product landing page did mention Progyny Health Insurance Company of Washington. So I pulled the thread. Washington state incorporation records showed the name had been reserved in August 2024. Six months later, in February 2025, the entity was formally incorporated. By July 2025, Progyny Health Insurance Company of Washington had been admitted as an active health insurer by the Washington Office of Insurance Commissioner. In the second half of 2025, they filed their first few products with the regulator, all still sitting in review on the SERFF database as of July 2026. The filings also make nationwide coverage ambition explicit. So this has been stewing since August 2024, the date the name was chosen. I went on LinkedIn to check if they had any actuaries on the team. They hired an actuary in April 2023, and a second in January 2026 (who specializes in pricing insurance products) three months before the launch. 

The announcement that the press called a product launch had been a strategic transformation at least three years in the making. The SEC filings hinted at it. These four signals — an actuary hire, a name reservation, an insurance license, and active product filings with a state regulator — were sitting in plain sight the whole time. For anyone watching, just one of those foreshadowed what was coming.

I’ve been watching the market reaction since the launch. The move is still being read as market expansion downward, when it’s really business model innovation.

Why become an insurer at all?

Continue reading…

Matthew reviews ChatGPT Health

OpenAI just made ChatGPT Health generally available. This is their partnership with B.Well which allows you to bring your data from various EMRs into chatGPT. So I took it for a spin–Matthew Holt

Value Is in the Eye of the Beholder

By KIM BELLARD

The most (unintentionally) amusing story I read this week was Tim Higgin’s Wall Street Journal article Alex Karp Is Saying What Every Angry CEO Is Thinking About AI. Dr. Karp (yes, he has a Ph.D.), co-founder and CEO of Palantir Technologies, is upset about how AI companies are using relationships with their business customers to harvest data and business insights from those customers. “Something has gone completely wrong,” he fumed.

Now, this is Palantir, mind you; it may not have invented surveillance capitalism but it might have perfected it. It has become essential to government and large corporations across the world. Most of us are aware of how tech companies like Meta or Google give us “free” services that exist primarily to collect more data on us, which they then use to target ads to us, but Palantir’s data collection and analysis operate at a level we often don’t recognize.  But make no mistake; it is using our data, and not necessarily in our best interests.

Mr. Higgins quotes former White House AI czar David Sacks in support of Dr. Karp’s concerns:

Anthropic has launched Claude Science, Claude Security, Claude Legal, and of course Claude Code—each expanding into categories previously served by companies building on top of their models. The pattern is consistent: Watch where value is being created, then move in directly. Dominate the model layer, then use that position to capture the most lucrative verticals.

So it is delicious irony that Dr. Karp and others are finding themselves at the wrong end of the power inequality with their data.

I find myself thinking about healthcare when I think above this new wave of data collectors/ synthesizers. It seems pretty clear that the AI companies aren’t going anywhere, and are expected to reshape most industries, including healthcare. Lots has been written about AI’s use in healthcare, including by me. It is both inevitable and, in many cases, desirable. Now this issue of AI’s insatiable appetite for data makes me wonder if we’re looking at things wrong.

I’ve worked in healthcare for longer than I care to admit, and at no point did people not complain that healthcare in general, and health insurance in particular, was too expensive. And yet, costs have kept rising. We’re closing in on $6 trillion in U.S. healthcare expenditures. No matter what kind of health insurance you have – large employer, small employer, ACA Marketplace, Medicare Advantage, even Medicare Supplements for traditional Medicare – your premiums (and/or out-of-pocket costs) are likely going up at rates we haven’t seen in years.

Two well known facts about rising costs are, one, that it is not so much we’re using too many services as it is that Americans pay way higher prices for healthcare than in most countries, and, two, that a relatively small percentage of people account for the vast majority of healthcare spending. The latter has an insidious effect on health insurance premiums, as people with fewer expenses are less likely to have or keep health insurance, making premiums for the remaining people higher. Nobody wants to pay for the people who use a lot of health care, but they want other people to help pay if they end up being one of those people. It’s a conundrum.

Now, optimists hope that AI can do a better job of identifying all the wasted, unnecessary, or inappropriate care we use – estimated as much as one-third – and help make administration more efficient; current levels are estimated as 15-30% of spending. Good goals, both of them, and it is entirely plausible that AI can help with both. But it would still remain that sick people are the “problem” with our health care spending and health insurance premiums, and I want to propose a different way of looking at them.

Continue reading…

The wrong people are scared of clinical AI

By CRAIG HAUBEN

Ask anyone outside healthcare who resists clinical AI and you’ll get a confident answer. The older doctors. The ones who spent thirty years building expertise and now see a machine coming for it. The story writes itself, which should have been the first clue it was wrong.

I’ve spent thirty years in healthcare, and I now run a company that builds and runs AI inside provider and payer organizations. At Clutch we use AI’s data analysis to solve engagement challenges. Who is the patient today? What message will land with them? When do they want to read it? Get those right and you can drive the kind of sustained behavior change that moves clinical outcomes like drug adherence, care plan adherence, and gap closure.

So I’m not working from theory. I watch this land in real workflows, and here’s what I see. The clinicians most enthusiastic about AI are usually the ones who’ve done the job the longest. The resistance comes from somewhere else. If you run a health system, that difference should change how you plan your next deployment.

Start with the adoption numbers, because they already break the resistance story. The AMA’s latest survey found four in five physicians now use AI in practice, up from 38 percent in 2023. That’s not a profession digging in against a threat. That’s a profession that found something useful.

Now the veterans. A doctor with three decades in a specialty can see, better than anyone, what these systems are good at. Pattern recognition at scale. Catching the thing that should have been flagged two visits ago. Surfacing what was already sitting in the data: the missed finding in last year’s imaging, the lab trend across eighteen months that looked unremarkable one value at a time, the three ED visits in six weeks nobody had the time to connect.

This isn’t hypothetical. The Nature study of Google’s breast cancer screening system showed a 9.4 percent drop in false negatives for US patients, the cancers human readers missed. The largest NHS evaluation to date, across 175,000 women, found AI caught more invasive cancers with fewer false positives than human readers. The harm these systems go after, information that existed and never got connected, is one experienced clinicians know cold. They’ve spent careers watching its absence hurt people.

Here’s one from our own work. We’re working with a national government programs payer on some of their hardest members to engage, the high intensity ones who need contact four or five times a day for six months or more. We got engagement to 95 percent, measured by the customer, and adherence to 93 percent. The result was a 0.8 average drop in HbA1c and an 18 percent reduction in symptoms.

When a system takes the mechanical load off so the judgment work gets more attention, the thirty-year clinician doesn’t feel threatened. They feel relieved. Their expertise is the judgment, not the data retrieval, and they’ve always known the difference.

Now look at where the fear actually lives. It comes from the middle.

Continue reading…

Future of AI and Telehealth in primary care — Panel discussion

A couple of months back I hosted a conversation about my favorite topics, primary care and how telehealth and AI are changing it. The panel was Timm Schneider — Co-Founder & COO, Third Way Health, Jamie Reddick — COO, Graybill Medical Group & Erin Parks, Ph.D. — Co-Founder, Equip. The panel was at a tech heavy conference called TechCon Global in San Diego. Sadly the weather stopped us getting Matt Siegler from Akido Labs. We got into it about tech. incentives, specialty care and the role of AI in access and patient support–Matthew Holt

How Online Prescription Services Are Closing the Access Gap for Patients Who Skip the Doctor’s Office

By DAMIAN WONJO

Every clinician keeps a private list of the patients they don’t see. Not the ones who cancel, the ones who never book. The shift worker who reschedules the same appointment three times and then quietly gives up. The parent who can’t justify half a day off and a waiting-room afternoon for a routine refill. The patient whose condition carries enough stigma that the friction of a face-to-face visit becomes, in itself, a reason to do nothing. These people don’t show up in no-show statistics. They show up later, as complications, as emergencies, as avoidable deterioration.

This is the access gap, and from where I sit as a physician in Europe, it has less to do with the raw supply of doctors than with the cost of reaching one, measured not only in money but in time, distance, and effort. When that cost climbs higher than a patient’s tolerance, care simply doesn’t happen. Online prescription services and remote consultation won’t fix every part of this problem. But they target precisely the variable that most reforms ignore, which is friction.

The patients who fall through

It is tempting to frame telemedicine as a convenience for the already-healthy and already-connected. In practice, the people who benefit most are often those with the least slack in their lives. A patient stabilised on the same antihypertensive for three years does not need a fresh diagnostic odyssey to continue it, they need a prescription before they run out. A working adult who recognises a recurring, familiar problem does not always need a physical examination to be helped safely. Forcing every such encounter through the narrow door of an in-person appointment does not raise the standard of care, it raises the rate at which people abandon it.

Continuity is where this matters most. Chronic conditions are managed in refills, and a missed refill is not a clerical event but a gap in treatment with real physiological consequences. Lowering the barrier to that refill is not a luxury. It is, quietly, one of the highest-yield interventions available.

What changed in Europe

The pandemic did not invent telemedicine, but it normalised it, and it accelerated the infrastructure underneath it. Poland is a useful case study. Electronic prescriptions became the national standard in 2020, and today essentially every prescription is issued digitally, retrievable by the patient through a government health account and dispensable at any pharmacy with a code. The clinical encounter and the prescription were decoupled from a single physical location without being decoupled from a licensed prescriber.

That distinction is the whole argument. A responsible online prescription service is not a vending machine. It is a licensed physician, working within the same legal and ethical framework as any clinic, using a different channel to reach the patient. The technology is mundane. The consequence, that a patient who would otherwise have gone without is now seen, is not.

Continue reading…

A ridiculously stupid letter from a health insurer

By MATTHEW HOLT

It’s hard to imagine but I may now be in possession of the stupidest letter I’ve ever received from an American health insurance company–-and I’m the guy who got five identical letters on one day from Blue Shield of California telling me that they had changed my primary care doctor when I had initiated the change.

A little backstory.  As those you’ve been following along with my various telenovelas may remember that last year I was diagnosed with a failing heart valve.  I also have a failing left knee due mostly to snowboarding into a tree 24 years ago.

I was attempting to put off doing anything about the heart valve for as long as possible because it sounds painful and unpleasant, and I was hoping that I could go ahead with a knee replacement so that my snowboarding can continue apace. My doctors are at UC San Francisco and they agreed that I should have the knee replacement on July 6th, assuming that my heart valve had not got much worse. On June 16th I went into UCSF for a bunch of knee replacement pre-workup and they also checked my heart.

However, my new insurance company, thanks to my wife’s new job, is Cigna. Those of you in California may know that Cigna was having a big dispute with the University of California Health system and that its contract with them was due to expire on June the 30th of this year. Why a health plan and a big provider organization have contracts that expire in the middle of the year when the employers and people who use the health plan network buy them on an annual basis starting in January I don’t know –  and it’s ridiculously stupid. But let’s not get distracted cause I’m not talking about that here!

Because of the fact that they’d be out of network, the ortho team made the obvious suggestion that I move the knee replacement a little earlier, In fact it was planned for June the 22nd. This did not upset me too much as you may have seen that some corrupt Italians have organized a soccer tournament that would give me plenty of games on TV to be entertained by while I was lying around recovering.

Sadly one of the pretests I had on June 16th was an echocardiogram that indicated that my heart valve was in even worse shape than it had been earlier in the year.  After quite a lot of back and forth between the cardiac team, the knee team and the anesthesia team, everyone agreed to put off the knee surgery until we figured out my heart.

Meanwhile sometime late on Thursday the 25th or early on Friday the 26th of June, UC Health and Cigna stepped back from the brink and came to an agreement that will continue the UC system being in Cigna’s network.

Which all brings me to July 6th when I received a letter from Cigna

This is the one that contains more stupidity per square inch than any other communication I’ve had from an insurance company.

Continue reading…

Life Not As We Know It

By KIM BELLARD

Well, let’s see. Last week much of the U.S. and parts of Europe were under a crippling heat dome. The U.S. celebrated its 250th birthday. And there’s something called the World Cup going on, for those of you who care about such things. But, I mean, really, the news of the week? SpudCell.

OK, maybe you missed that one. If you are not a fan of science, or of synthetic biology in particular, news about it might not have shown up in your feeds, or perhaps you thought it was another ploy by the Potato Association of America to get you to buy even more potatoes. SpudCell is something truly new: “the world’s first synthetic cell with a complete life cycle, built entirely from non-living chemical components.”

Take a minute to take that description in.

“SpudCell performs the behaviors often used to tell the living from the inert — it feeds, grows, replicates its genome, divides and undergoes selection — yet it is far simpler than any natural cell and was assembled, part by part, by hand,” the project researchers wrote in a statement.

It was designed and built by researchers at the University of Minnesota, announced last week along with a preprint of their paper.The team was led by Professor Kate Adamala, and the name is either due to its supposed resemblance to a potato or it’s a play on “Sputnik.”

“This is likely the most exciting project I’ve ever worked on,” said Professor Adamala. “We’ve replicated in chemistry what only used to be possible in biology: the complete set of behaviors of a cell. It proves that the most fundamental functions of life, like growth and replication, do not need a mysterious magical spark.”

Scientists have been working for decades on stripping away genetic material from living cells to try to find the minimum necessary for life, but Professor Adamala and her team went the other way, gradually building up genetic material until it started behaving in ways we’d expect cells to.

The impressive thing is that the team engineered everything SpudCell does. As The Economist put it: “Everything the resulting cells do, they do because of molecules that Dr Adamala’s team put there. That leaves no room for mysteries.” That’s not true when researchers start with living cells.

Drew Endy, a synthetic biologist at Stanford University, told Carl Zimmer of The New York Times, “It’s a cell that was built, not born. It’s constructed, but it does what cells do.”

SpudCell is very basic.

Continue reading…



