Categories

Category: The Business of Health Care

What Good Is Health Coverage If You Cannot Get to the Doctor

By JOE MKHITARYAN

We spend a lot of time talking about who has health insurance. I think we need to spend more time asking who can actually use it.

You can approve an appointment, find a specialist and cover the treatment. But if the patient cannot get out of the house and into the right vehicle, none of that gets them to the doctor.

I have been in the medical transportation business since 2010. I built my businesses in Southern California, where a few miles on a map can turn into a long trip in traffic. Running these operations has taught me to ask questions that are easy to miss when you are looking at a transportation budget.

Can the patient walk? Can they sit upright? Are there stairs outside the home? Do they need a wheelchair vehicle or a gurney? Who is bringing them back?

Those answers determine whether the ride will work. They need to be settled before a vehicle arrives.

Non-emergency medical transportation, or NEMT, is how many patients reach appointments when they cannot get there on their own. It is easy to describe it as a ride. Providing it is more involved.

Take a gurney trip. In our operation, that means sending two staff members. They have to help the patient safely, load and secure the gurney, make the trip and complete the handoff. Then there is the return. That crew is working well before the vehicle starts moving and after it stops.

If you price that trip mainly by the miles driven, you leave a lot of the work out of the calculation.

I pay attention to this because I am the one paying wages, insurance and vehicle expenses. I have a business interest in the rates. But anyone responsible for patient access should care whether those rates can support the service they expect. You cannot keep asking for trained staff and dependable vehicles without considering what it costs to provide them.

Of course, paying more does not automatically produce better service. Providers should have to show that they are safe, reliable and doing the work they bill for. The question is whether the payment and the expectations make sense together.

The need is real.

Continue reading…

Employers that exclude GLP-1s point staff to a website and a pretax account

By JOHN SAMARAS

Most employers still won’t cover GLP-1s for weight loss, and some of them now tell the employee where to buy them without the plan. The International Foundation of Employee Benefit Plans’ 2026 survey, published in July, found that 60 percent of employers cover the drugs for diabetes only and 36 percent for both diabetes and weight loss. Among the employers that exclude weight loss, 27 percent steer employees to a direct-to-consumer platform and 21 percent to their FSA, HSA or integrated HRA.

The same survey shows why. For its respondents, GLP-1s went from 6.9 percent of annual claims in 2023 to 11.4 percent in 2026. In a Business Group on Health survey reported by Reuters in June, 10 percent of large employers that cover them plan to drop them in 2027. Cigna stopped covering them for its own employees in July.

What the employee walks into

I record the published cash price of every US GLP-1 telehealth program every Monday, and this is the market those employees are sent to. At the maintenance dose, Novo Nordisk sells its Wegovy pen direct for $349 a month and its Wegovy pill for $299. The pill’s $149 price covers only the starter doses. The cheapest month on my chart, checked September 28, 2026, is $149 with auto-refill for compounded semaglutide, a pharmacy-made version that is not FDA-approved and is not Wegovy or Ozempic.

The tax treatment is one sentence in IRS Publication 502: you can include “amounts you pay to lose weight if it is a treatment for a specific disease diagnosed by a physician (such as obesity, hypertension, or heart disease).” Prescribed drugs qualify. The 2026 limit on a health FSA is $3,400.

Run through an FSA, a $149 month costs an employee in the 22 percent bracket about $105, because the dollars skip federal income tax and the 7.65 percent payroll tax. The employer skips its own 7.65 percent on the same dollars. The federal government gives up that revenue on a drug the plan declined to cover.

The tax break has no formulary

A covered drug passes through a formulary, a prior authorization and a pharmacy network. The cash benefit passes through none of them. Publication 502 turns on whether a drug was prescribed, and a compounded product qualifies on the same terms as a branded pen.

Continue reading…

Wall Street in the ER: How Private Equity Is Squeezing Local Hospitals

By ADAM LEE

Reflecting on a Private Equity (PE) internship in New York City reveals a major takeaway: financial engineering can be incredibly empowering, but applying it to public infrastructure often catches vulnerable communities in the crossfire.

The PE industry typically views the world through balance sheets, debt structures, cash flow optimization, and lucrative acquisitions. While these principles generate immense profit on paper, applying them to local healthcare—specifically safety-net hospitals—creates severe real-world tradeoffs.

Here are the major takeaways regarding the intersection of healthcare and business.

1. How Hospitals Get Saddled with an LBO

In the PE world, a Leveraged Buyout (LBO) is the primary acquisition method. An LBO pushes the debt onto the acquired asset, similar to convincing a bank that a newly purchased home will pay off its own mortgage.

For hospitals, this process typically follows a specific pattern:

  • The PE firm borrows huge sums to purchase a hospital and its infrastructure.
  • That borrowed debt lands directly on the hospital’s balance sheet.
  • The firm sells the hospital’s land and buildings to a real estate company for quick cash.
  • The hospital is left paying rent (with built-in escalators) just to operate inside its own building via a sale-leaseback arrangement.

The clearest example is Steward Health Care.

Continue reading…

Time to Stop “Calling it Reimbursement”

By JEFF GOLDSMITH

Back during the Jurassic period, at the beginning of my consulting career, senior colleagues at Ernst and Whinney took me to lunch to explain to the newby the facts of life in healthcare finance. The biggest takeaway from that long ago conversation: the entire history of hospital finance was built up on the revenue side. Managing costs was simply too challenging for most C-suites, because it inevitably required involvement with medical staffs who, at the time, were independent practitioners and beyond the hospital’s direct control. Therefore, the job of payers-governments and private insurers- was to “reimburse” hospitals for their expenses (that is, so long as the costs were “allowable”). The subtext of using the term “reimbursement” was : “We already spent the money and you owe us!”

In 2026, this mindset miraculously persists. This is despite the fact that Medicare, the largest and most influential payor for hospital services, has not reimbursed hospitals for the cost of inpatient care for more than forty years and for outpatient services in more than twenty! And the rest of the payment system is rebelling against the role as the residual payer for the hospital’s “unreimbursed” expenses.

The result of three generations of managements trained to these expectations is akin to football players who only trained their upper bodies and left the lower bodies to nature. Catching the ball is one thing; blocking and tackling with no lower body leverage is quite another.

Today’s C-suites lack the reflexes, management information and cultural support to respond substantively to the damaging blow that is HR 1, which will both reduce dramatically Medicaid payment and increase the number of uninsured patients by as much as 14 million. Controlling expenses today means engaging clinicians-physicians and nurses-and altering their workflows, staffing and incomes, a political nightmare for many managements.

The “reimbursement” mindset is a huge handicap standing between current leadership and actual control over their operations. For those in an indefensible cost position, it is so much easier to give up ownership, merge with a larger system and let someone else unburdened by local socio-political constraints and perhaps with better management controls clean up their extensive agenda of unfinished business. The reluctance of legacy managements to actually cut costs is a hidden contributor to the industry’s continuing consolidation.

Those who pay for care have had enough. The ability of care system leaders to shift those unmanaged costs onto the dwindling collection of full bore commercial payers is coming to an end. Commercial insurers are no longer willing to fund all the hospitals “unreimbursed” costs. Angry progressive policymakers and academics, egged on by Arnold Ventures, are agitating in state legislatures to cap commercial rates as a percentage of Medicare.

Sooner or later, hospital managements will take ownership of their piece of the healthcare affordability challenge. And they will be getting up early to hit the gym . . . and build the strength, balance and muscle memory to manage their entire business, not just their revenues.

Jeff Goldsmith is a veteran health care futurist, President of Health Futures Inc and regular THCB Contributor. This comes from his personal substack.

The pharmacy pays $1,302. The patient pays $299

By JOHN SAMARAS

A US retail pharmacy pays $1,302 to acquire one month of branded Wegovy. That figure comes from the Centers for Medicare and Medicaid Services National Average Drug Acquisition Cost file, effective August 19, 2026, for the 25 mg oral tablet at 30 tablets a month.

The cheapest cash price I verified on a seller’s own published page, for the same month of the same product, is $299. That is oral Wegovy at the maintenance dose, at Sam’s Club Member Health, which sells at the manufacturer’s published self-pay price, checked August 31, 2026.

The two numbers are more than a thousand dollars apart.

Where the second number comes from

Every Monday I check what each US GLP-1 telehealth program publishes as its price, on the program’s own page, and record it. Not the advertised starting rate. Not the prepaid annual plan divided by twelve. The all-in monthly cost of staying on the drug at a maintenance dose.

This month that record turned into an index. Across a fixed panel of 11 programs the median all-in price was $348 a month in August, the same figure in all five weekly checks. It did not move against July.

One program cut its price in August and none raised one. GoodRx for Weight Loss went from $388 to $338 on August 31, and it sits outside the panel. Three other apparent cuts in the record were mine rather than the programs’. Ivim Health and Sesame Care were sitting on prepaid plan rates, and my Costco through Sesame row was carrying $408 for a plan that was $398 all month. Putting each on the rate a reader can start on today lands in the series as a step. The revision log on the September release itemizes all three. The cheapest verified compounded semaglutide route held at $178 a month, at Mochi Health, which posts one flat all-in price at every dose. Sam’s Club Member Health was the cheapest verified branded route at $299 for the Wegovy pill. Both figures were checked on August 31, 2026.

The method fits in a paragraph. For the floors, take the lowest published all-in price in each route on every Monday of the month, then take the median of those weekly lows. For the median, take the middle of the fixed panel each Monday, then the median of those five weekly figures. The panel is fixed on purpose, so a change in which programs I track cannot read as a change in price. The number sits at a dated URL and does not change after publication. A correction becomes a numbered revision with a note.

NADAC measures acquisition cost

The distance between $1,302 and $299 is not pharmacy margin. NADAC measures what pharmacies pay their wholesaler. It says nothing about dispensing costs, the clinician visit, shipping, or what a manufacturer charges through a channel it owns.

46brooklyn Research has published NADAC dashboards free since 2019, and every derivative here rests on their work. What I added is the join: their acquisition data against verified consumer cash prices, which nobody had put side by side.

The two prices sit in different channels. Insurance routes a patient into the pharmacy channel, where the $1,302 sits. The $299 is a cash price, paid by a buyer with no coverage.

The packaging gap

The same NADAC file holds a second finding. Lilly sells Zepbound both as single-dose pens and as a multi-dose KwikPen. At 15 mg, a pharmacy pays $672 a month for the KwikPen and $1,051 a month for the equivalent single-dose pens. The only difference is the container. The spread is 1.56x, or $379 a month. At the 2.5 mg starting dose it is $482 against $1,052, or 2.18x.

Why nobody else has this number

Prices in this category move weekly and nobody records them. A patient cannot tell an introductory rate from a maintenance rate. A reporter covering a price cut has no baseline to say whether it was a cut at all, and the only public numbers are the ones a manufacturer put in a press release.

The fix is somebody writing the price down every week and publishing the method with a version number on it.

Everything above is free to reuse under CC BY 4.0, with a link and no registration. The CSV and the JSON sit at https://glpchart.com/price-index/. If you want a different cut, by state, by drug or by program, ask and you will have it inside a day.

From October the release lands on the first Tuesday of the month. The next one is October 6, 2026.

John Samaras is the founder of GLP Chart, which verifies the cash price of every US GLP-1 telehealth program every Monday. He writes about price, coverage and market structure, and leaves the clinical questions to clinicians.


The same 10mg Zepbound costs $449 or $699

By JOHN SAMARAS

Eli Lilly sells a month of 10mg Zepbound for $449 through LillyDirect, its own pharmacy. That price holds only if you refill within 45 days of your last fill. Refill on day 46 and the same box is $699. The $250 is a late fee.

Here are the two ways to buy branded Zepbound that publish a cash price. Both ship Lilly’s single-dose vials from Lilly’s own pharmacy.

LifeMD prescribes Zepbound and fills it through the same LillyDirect. It charges $349 to $549 for the drug where Lilly charges $299 to $449, and bills $149 a month on top of that.

Zepbound is tirzepatide. Compounded semaglutide is a different molecule on a different price ladder. Of the 15 programs I track that dispense compounded GLP-1, five name the pharmacy that makes it. Ten do not.

Where you buy itPublished cash priceFee on top
Lilly direct, self-pay$299 at 2.5mg, $399 at 5mg, $449 at 7.5mg and abovenone
LifeMD$349 to $549 by dose$149 a month, $39 first month

FDA wrote to three of those sellers on February 20. It told Strut to stop selling its compounded drugs as “Generic Zepbound, Mounjaro.” It told Medvi to drop “Same active ingredient as Wegovy and Ozempic.” For Ivim the problem was the label. Printing “Ivim” on the vial implied Ivim had compounded the drug. It had not.

All three letters are about what the sellers wrote on a page.

I price these programs every Monday, and the Internet Archive holds what they charged before I started, so the letters have a before and an after. Strut advertised $149 for its starting-dose compounded semaglutide injection a month before its letter and publishes $149 today. Medvi has published $299 for compounded semaglutide refills at every Monday check since May 25.

None of the three letters required a program to name the pharmacy that fills the order.

John Samaras is the founder and editor of GLP Chart, which tracks what every major GLP-1 program charges, checked every Monday, and publishes its methodology. No program pays to be listed or ranked.

Healthcare Has Confused Disclosure With Understanding

By JOE FEGHALI

Healthcare has become very good at producing disclosures. It is much less good at producing understanding.

A hospital posts a price file. A health plan publishes negotiated rates. A provider gives an estimate. A patient portal contains a document somewhere. A consent form is signed. The box is checked.

But the patient may still not understand what they are being asked to approve, what the likely cost pathway looks like, or what happens when treatment changes.

This is the quiet failure of healthcare transparency. We have spent years trying to make prices more visible. That was necessary. But visibility is not the same as usability. A price that exists somewhere is not the same as a patient understanding the financial commitment they are making before care begins.

Price transparency matters. It is just not enough.

The next frontier is not whether healthcare can disclose more numbers. It is whether healthcare can explain what those numbers actually mean.

The price is rarely the product

Most consumer markets understand the difference between a price and a purchase. A flight price means one thing if it includes luggage and another if it does not. A construction quote means one thing if it includes materials, labor, permits, and cleanup, and another if each of those becomes an add-on.

Healthcare often asks patients to make decisions with less clarity than they would expect in much simpler markets.

The deeper problem is not only that prices are hidden. Sometimes the prices are visible. The problem is that the object being priced is unclear.

A patient does not experience healthcare as a billing code or a machine-readable file. A patient experiences healthcare as a journey: consultation, diagnosis, imaging, procedure, medication, facility involvement, follow-up, revision, complication, recovery, and sometimes a second opinion when the first pathway becomes confusing.

Yet transparency policy often focuses on isolated prices rather than the care pathway the patient is actually buying into.

Continue reading…

A ridiculously stupid letter from a health insurer

By MATTHEW HOLT

It’s hard to imagine but I may now be in possession of the stupidest letter I’ve ever received from an American health insurance company–-and I’m the guy who got five identical letters on one day from Blue Shield of California telling me that they had changed my primary care doctor when I had initiated the change.

A little backstory.  As those you’ve been following along with my various telenovelas may remember that last year I was diagnosed with a failing heart valve.  I also have a failing left knee due mostly to snowboarding into a tree 24 years ago.

I was attempting to put off doing anything about the heart valve for as long as possible because it sounds painful and unpleasant, and I was hoping that I could go ahead with a knee replacement so that my snowboarding can continue apace. My doctors are at UC San Francisco and they agreed that I should have the knee replacement on July 6th, assuming that my heart valve had not got much worse. On June 16th I went into UCSF for a bunch of knee replacement pre-workup and they also checked my heart.

However, my new insurance company, thanks to my wife’s new job, is Cigna. Those of you in California may know that Cigna was having a big dispute with the University of California Health system and that its contract with them was due to expire on June the 30th of this year. Why a health plan and a big provider organization have contracts that expire in the middle of the year when the employers and people who use the health plan network buy them on an annual basis starting in January I don’t know –  and it’s ridiculously stupid. But let’s not get distracted cause I’m not talking about that here!

Because of the fact that they’d be out of network, the ortho team made the obvious suggestion that I move the knee replacement a little earlier, In fact it was planned for June the 22nd. This did not upset me too much as you may have seen that some corrupt Italians have organized a soccer tournament that would give me plenty of games on TV to be entertained by while I was lying around recovering.

Sadly one of the pretests I had on June 16th was an echocardiogram that indicated that my heart valve was in even worse shape than it had been earlier in the year.  After quite a lot of back and forth between the cardiac team, the knee team and the anesthesia team, everyone agreed to put off the knee surgery until we figured out my heart.

Meanwhile sometime late on Thursday the 25th or early on Friday the 26th of June, UC Health and Cigna stepped back from the brink and came to an agreement that will continue the UC system being in Cigna’s network.

Which all brings me to July 6th when I received a letter from Cigna

This is the one that contains more stupidity per square inch than any other communication I’ve had from an insurance company.

Continue reading…

Schrodinger’s Co-pay

By MATTHEW HOLT

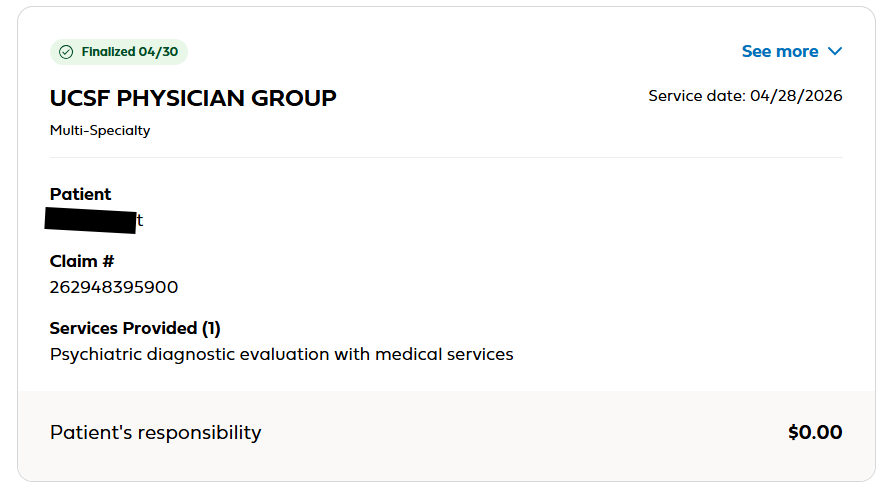
More tales of the woes of dealing with health insurance. I live in Marin County, California and one of the things that comes with that is a diagnosis of ADHD for my children. (OK, I have made that joke before but it is true!). My kids now visit a psychiatrist for more sophisticated med management than they receive at their pediatrician. We were (until recently) on a Blue Shield HMO via the Covered California exchange. 

While I was at the doctor’s office, I talked to the staff. They told me I owed a $50 copay. I didn’t pay them (yet) and I went online and saw the claim

The reasonable, informed consumer might think that I owed nothing. The clue being that
“Patient Responsibility” was $0.

But if you click the “See More” in the top right it shows you this

You probably still think that I owe $0. But if you add the numbers on the right you might notice they don’t total $0.

Continue reading…

Adventures in health care billing. My $51.96 zit co-insurance

By MATTHEW HOLT

I know my many fans love me delving into the world of why we get seemingly incorrect trivial bills in health care, and what they all mean. The long telenovella of the $39.94 bill from Labcorp is as yet stalled with One Medical apparently resubmitting the original claim with the new preventative codes on it. But even though I am continuing and expanding my role as a difficult patient this year, there are still some blasts from the past that won’t quite leave.

This particular one concerns some rather unpleasant dermatology issues. For many years I had an nasty small sore/lesion on my leg that never quite healed. Then I started getting a few more that started as zits and never quite left. My wise PCP Andrew Diamond at One Medical told me to use some antibiotic wash and referred me to a dermatologist. Unfortunately the one I was referred to was out of network for the Blue Shield HMO I was in, but one request back to One Medical and I was both sent to a dermatologist in my network and got a pre-auth in the mail from Blue Shield to go see him!

Dr Cristian Gonzalez took a quick look at my leg, decided what the problem was, and  proceeded to inject, freeze and attack my various lesions. He then prescribed a cheap topical  steroid for me to use, and basically after 4 visits over the summer and Fall, my legs went back to resembling a baby’s bottom–well more or less. 

For each specialty visit Blue Shield had a co-pay of $85 per visit, which I handed over using my HSA card. One time the front desk said I had a balance, but when I asked them what it was for they told me it was a mistake. Until this week.

Some 4 months after my last visit I got a bill in the mail for $51.96

Given that I had made a co-pay of $85 each time, this seemed a little odd. So I took a look at my Blue Shield EOBs. (BTW they are back online, you may recall they vanished when Blue Shield cancelled and then changed my plan but the Internet never forgets….)

There a curious anomaly began to play out. Each visit generated three identical claims and three more or less identical EOBs.

Continue reading…