Categories

Above the Fold

Explaining My Scan and Reading It Are Different Jobs. AI Keeps Merging Them.

By LORENZO GIUNTINI

For years, I was the person leaving a medical appointment with another scan, another report, and too many unanswered questions. Chronic pain has a way of making every unfamiliar word feel urgent. I did not need a machine to replace a radiologist. I wanted someone to explain what the existing medical record was telling me, in language I could actually understand.

That desire led me to build a patient-facing imaging AI tool. Along the way, it also revealed a problem that healthcare AI has not clearly named: explaining an interpretation and creating a new interpretation are different jobs. We keep packaging them as though they were the same service.

If I upload a radiologist’s report and ask, “What does this mean?”, the task is to translate, contextualize, and clarify an existing professional interpretation without changing its meaning. If I upload MRI images and ask, “What is wrong with me?”, the task is different. The system is being asked to interpret primary medical evidence. Both experiences may look identical on a screen: a chat box, a reassuring tone, and paragraphs in plain English. But they do not deserve the same trust merely because they share an interface.

The health record became accessible before it became understandable

Patients are increasingly able to see reports without waiting for a conversation with a clinician. That is a major gain in autonomy. It is also often the moment when ordinary people discover how much of the medical record was written for another audience.

In July 2026, the Radiological Society of North America described research on AI-generated simplifications of radiology reports. The research suggested that simplified reports could improve patient comprehension and reduce anxiety in a vignette-based survey. That is an encouraging result for the report-explanation task. It is not evidence that the same system can accurately interpret an MRI or CT from image data.

The difference sounds obvious when spelled out. In practice, however, it can disappear within one conversation. A patient begins by asking what the report means. Then comes a photograph of the scan, or a request to find something the doctor may have overlooked. Suddenly the system has shifted from explaining known findings to generating new ones, often without a visible change in its claimed role.

Continue reading…


Three Agencies Could Define GLP-1 Friendly. None Has.

By HANA KAHLEOVA

Almost every week, a patient asks me some version of the same question. If drugs like Ozempic work by copying a hormone my gut already makes, can the right food do what the injection does?

Food and supplement marketers have already answered yes. Frozen dinners now carry GLP-1 Friendly badges. Supplement ads promise the drug’s effects in a capsule. Hundreds of products invoke the hormone, aimed at the roughly 12 percent of U.S. adults who have taken one of these medications. Yet the term has no federal definition. The U.S. Department of Agriculture, which has approved the phrase on some labels, has stressed that its approvals do not create a standard. In March, Kyle Diamantas, then the Food and Drug Administration’s top food official and now its acting commissioner, told Bloomberg Law the agency was aware of the issue but had no action planned.

The result is a marketing claim that borrows the name of a hormone, falls between three regulators and has been tested by none of them. For a health system still deciding who should get these drugs and who should pay for them, that is not a side issue. It shapes what patients think they can buy instead.

What the Science Supports

As a clinical researcher who studies diet and type 2 diabetes, I think the honest answer is more interesting than the label. Food really can raise the body’s own GLP-1. The hormone is released by cells lining the intestine within minutes of a meal and, hours later, in response to compounds gut bacteria make from fiber.

But the evidence does not support single-ingredient claims. A scoping review published in July gathered 52 trials of isolated fibers. Most tested a single dose, the typical trial enrolled 19 people, and fewer than a third found any rise in GLP-1.

The strongest signal my colleagues and I have found came from a whole meal. In a randomized crossover trial, 60 men, 20 of them with type 2 diabetes, ate two breakfasts with the same calories and proportions of carbohydrate, protein and fat: a tofu burger with green tea, or a processed pork-and-cheese burger with a sweetened latte. After the plant-based meal, GLP-1 secretion was 30.5 percent higher in the men with diabetes, and measures of insulin secretion and beta-cell function improved. The meals also differed in fiber, saturated fat and sugar, so we cannot say which difference mattered. What moved the hormone was a pattern of eating, not a molecule.

Continue reading…

Physicians Already Vet AI Tools. Regulation Should Let Them.

By POUYAN GOLSHANI

The Food and Drug Administration is now deciding how to regulate generative AI-enabled medical devices, tools that accept open-ended inputs, produce variable outputs and are often built on third-party foundation models. Its discussion paper asks the right questions. The best evidence for answering them comes from the specialty that has lived with regulated AI the longest. Of 1,430 AI-enabled device authorizations on the FDA’s public list from 1995 through 2025, 1,094 (76.5 percent) were reviewed by the radiology panel, and radiology, cardiovascular and neurology together accounted for 90.6 percent, according to a peer-reviewed analysis I co-authored. Annual authorizations rose from about 1.8 a year to 264 a year. Not one was recorded under a psychiatry panel.

Radiology’s experience points to one lesson above the others: requirements beyond what safety demands limit access, growth and innovation. The technology moves fast. A tool that is only somewhat useful today may improve access and care tomorrow, but only if it is allowed into the real world to prove itself. Too often we lead with product safety at the expense of innovation. Safety matters, but for tools that a clinician reviews before acting, and that do not run autonomously or change what the clinician can see in the underlying study, the responsibility should rest with the practices that use them, not with a premarket review modeled on drugs.

Why radiology went first

Radiology had the conditions that made AI buildable: images that were already digital, a common file standard and systems that route each study to the physician who interprets it. The authorization data describe this pattern; they do not establish its cause, and they measure authorizations, not adoption or patient benefit. The FDA also notes that its list is not comprehensive.

The data also show who brings these products to market. Of 740 companies, 502 (67.8 percent) had a single authorized device, while 13 companies accounted for 17.3 percent of devices. Many are single-product innovators building one software tool or one AI-enabled imaging device. Requirements that a multinational corporation absorbs easily often cannot be absorbed by them, and good ideas do not come only from incumbents.

Physicians are the real-world test

This is the point I most want regulators to hear. Reviewing an AI tool like a drug misreads who uses it. Drugs are consumed by patients, who may never report back. AI tools used in clinical practice are consumed by physicians, who notice quickly when a tool does not help and stop using it. I have watched FDA-cleared products abandoned within weeks because they were not useful in practice. Developers and their founders have their reputations at stake, and clinicians already monitor new products during rollout, authorized or not. Poor performers are noticed and dropped.

Congress has already accepted this logic once. The 21st Century Cures Act removed from FDA device oversight clinical decision-support software whose basis a clinician can independently review. The same reasoning should extend to computer-aided detection that a physician reviews and can override. A radiologist who sees a flag and disagrees with it should be free to override it, and should not be held to the high sensitivity, and sometimes low specificity, of a detection model. The standard of care should remain what other radiologists, or the clinicians who first see a scan, such as emergency physicians, would do, not what an overly sensitive algorithm flagged. The comparison is starker still because most studies in urgent care and emergency departments are first read by nonradiologists, and many outpatient scans wait days for a routine read.

Continue reading…

Jessica Holton, Ours Privacy

Ours Privacy was born from a particular problem that almost every digital health services company has — how do we identify the best customers without violating their privacy? CEO Jessica Holton explain to me what a pixel is, why so many hospitals and digital health companies have got in trouble, and how their solution actually improves information about customers, which is good for both the consumer and the healthcare company–Matthew Holt

This interview is part of a partnership between Ours Privacy and THCB.

Transcript

Matthew Holt: Hi, it’s Matthew Holt, The Health Care Blog. I have another THCB spotlight. I have with me today Jessica Holton. Jessica is the CEO of Ours Privacy. If you couldn’t tell, the name is behind her upper right shoulder over there. Jessica, welcome.

Continue reading…

The Mid-term Elections Will Not Resolve the Dysfunction at HHS

By STEVEN ZECOLA

Introduction.

The scientists at the Department of Health and Human Services (“HHS”) are breathing a sigh of relief given that the Democrats will be taking control of the House and Senate. For the past two years, there has been a tension within HHS between the scientific community and President Trump’s executive appointments. While Trump’s people have been “winning” the political battles over vaccines and restrictions on abortion-related treatments, they have not made much progress on modernizing the drug approval process, despite repeated promises. The approval process for promising therapies remains slow, uncertain, and resistant to change.

Managing by Press Release

Over the past year, HHS and FDA have announced initiatives involving personalized gene therapies, rare-disease development, AI-enabled healthcare, real-time clinical trials, and regulatory modernization.

Collectively, these announcements convey an agency committed to accelerating innovation. The more important issue for the public is whether these initiatives are changing how therapies move through the approval process.

From Promises to Practice

To judge whether reform is occurring, it is necessary to examine actual regulatory outcomes rather than public statements.

First, the FDA has had data for over a year showing how an innovative therapy for familial adenomatous polyposis (FAP) improves patient outcomes with minimum risk.

FAP is a genetic disorder that predisposes people to develop precancerous colon polyps. With FAP, patients will develop many colon polyps — typically over a hundred — starting at a young age. This significantly raises the lifetime risk that one of them will become cancerous. To manage this risk, healthcare providers usually recommend complete removal of the colon and sometimes the rectum, as well.

Continue reading…

340B’s Next Chapter Will Be Won (or Lost) on Data. Most Organizations Aren’t Ready.

By ADAM COHEN

The debate over the 340B Drug Pricing Program is complicated. However, beyond the arguments over rebates, contract pharmacies, and program intent sits a simpler reality that every stakeholder should plan around. Whatever form 340B takes next, the value an organization captures will depend on its ability to document and justify every discounted transaction with detailed, defensible data. Most organizations are not yet equipped to do that.

The stakes are rising, and so is the burden of proof

Covered entities purchased roughly $100 billion in outpatient drugs through 340B in 2025, according to the Health Resources and Services Administration (HRSA), nearly double the 2022 total. Hospitals and clinics use those savings to fund uncompensated care, rural access, and services for underserved patients. Manufacturers argue the program has outgrown its original intent and point to the duplicate discounts and diversion that HRSA audits have identified. Contract pharmacies are caught between manufacturer restrictions, state protections, and the litigation that followed.

HRSA’s revised rebate pilot, scheduled to begin in January 2027, establishes that instead of receiving the discount at the point of purchase, participating providers will pay more upfront, submit claims data, and receive the 340B price afterward. Providers are right to worry about cash flow and administrative load resulting from this shift. However, the more lasting change is where the burden now sits. Providers must prove eligibility, transaction by transaction, before they are made whole.

Continue reading…

Healthcare Is the Only Industry (Part 2)

Andrew Tsang

By ANDREW TSANG

(Part 1 is here)

The Healthcare Economy’s Smoking Gun

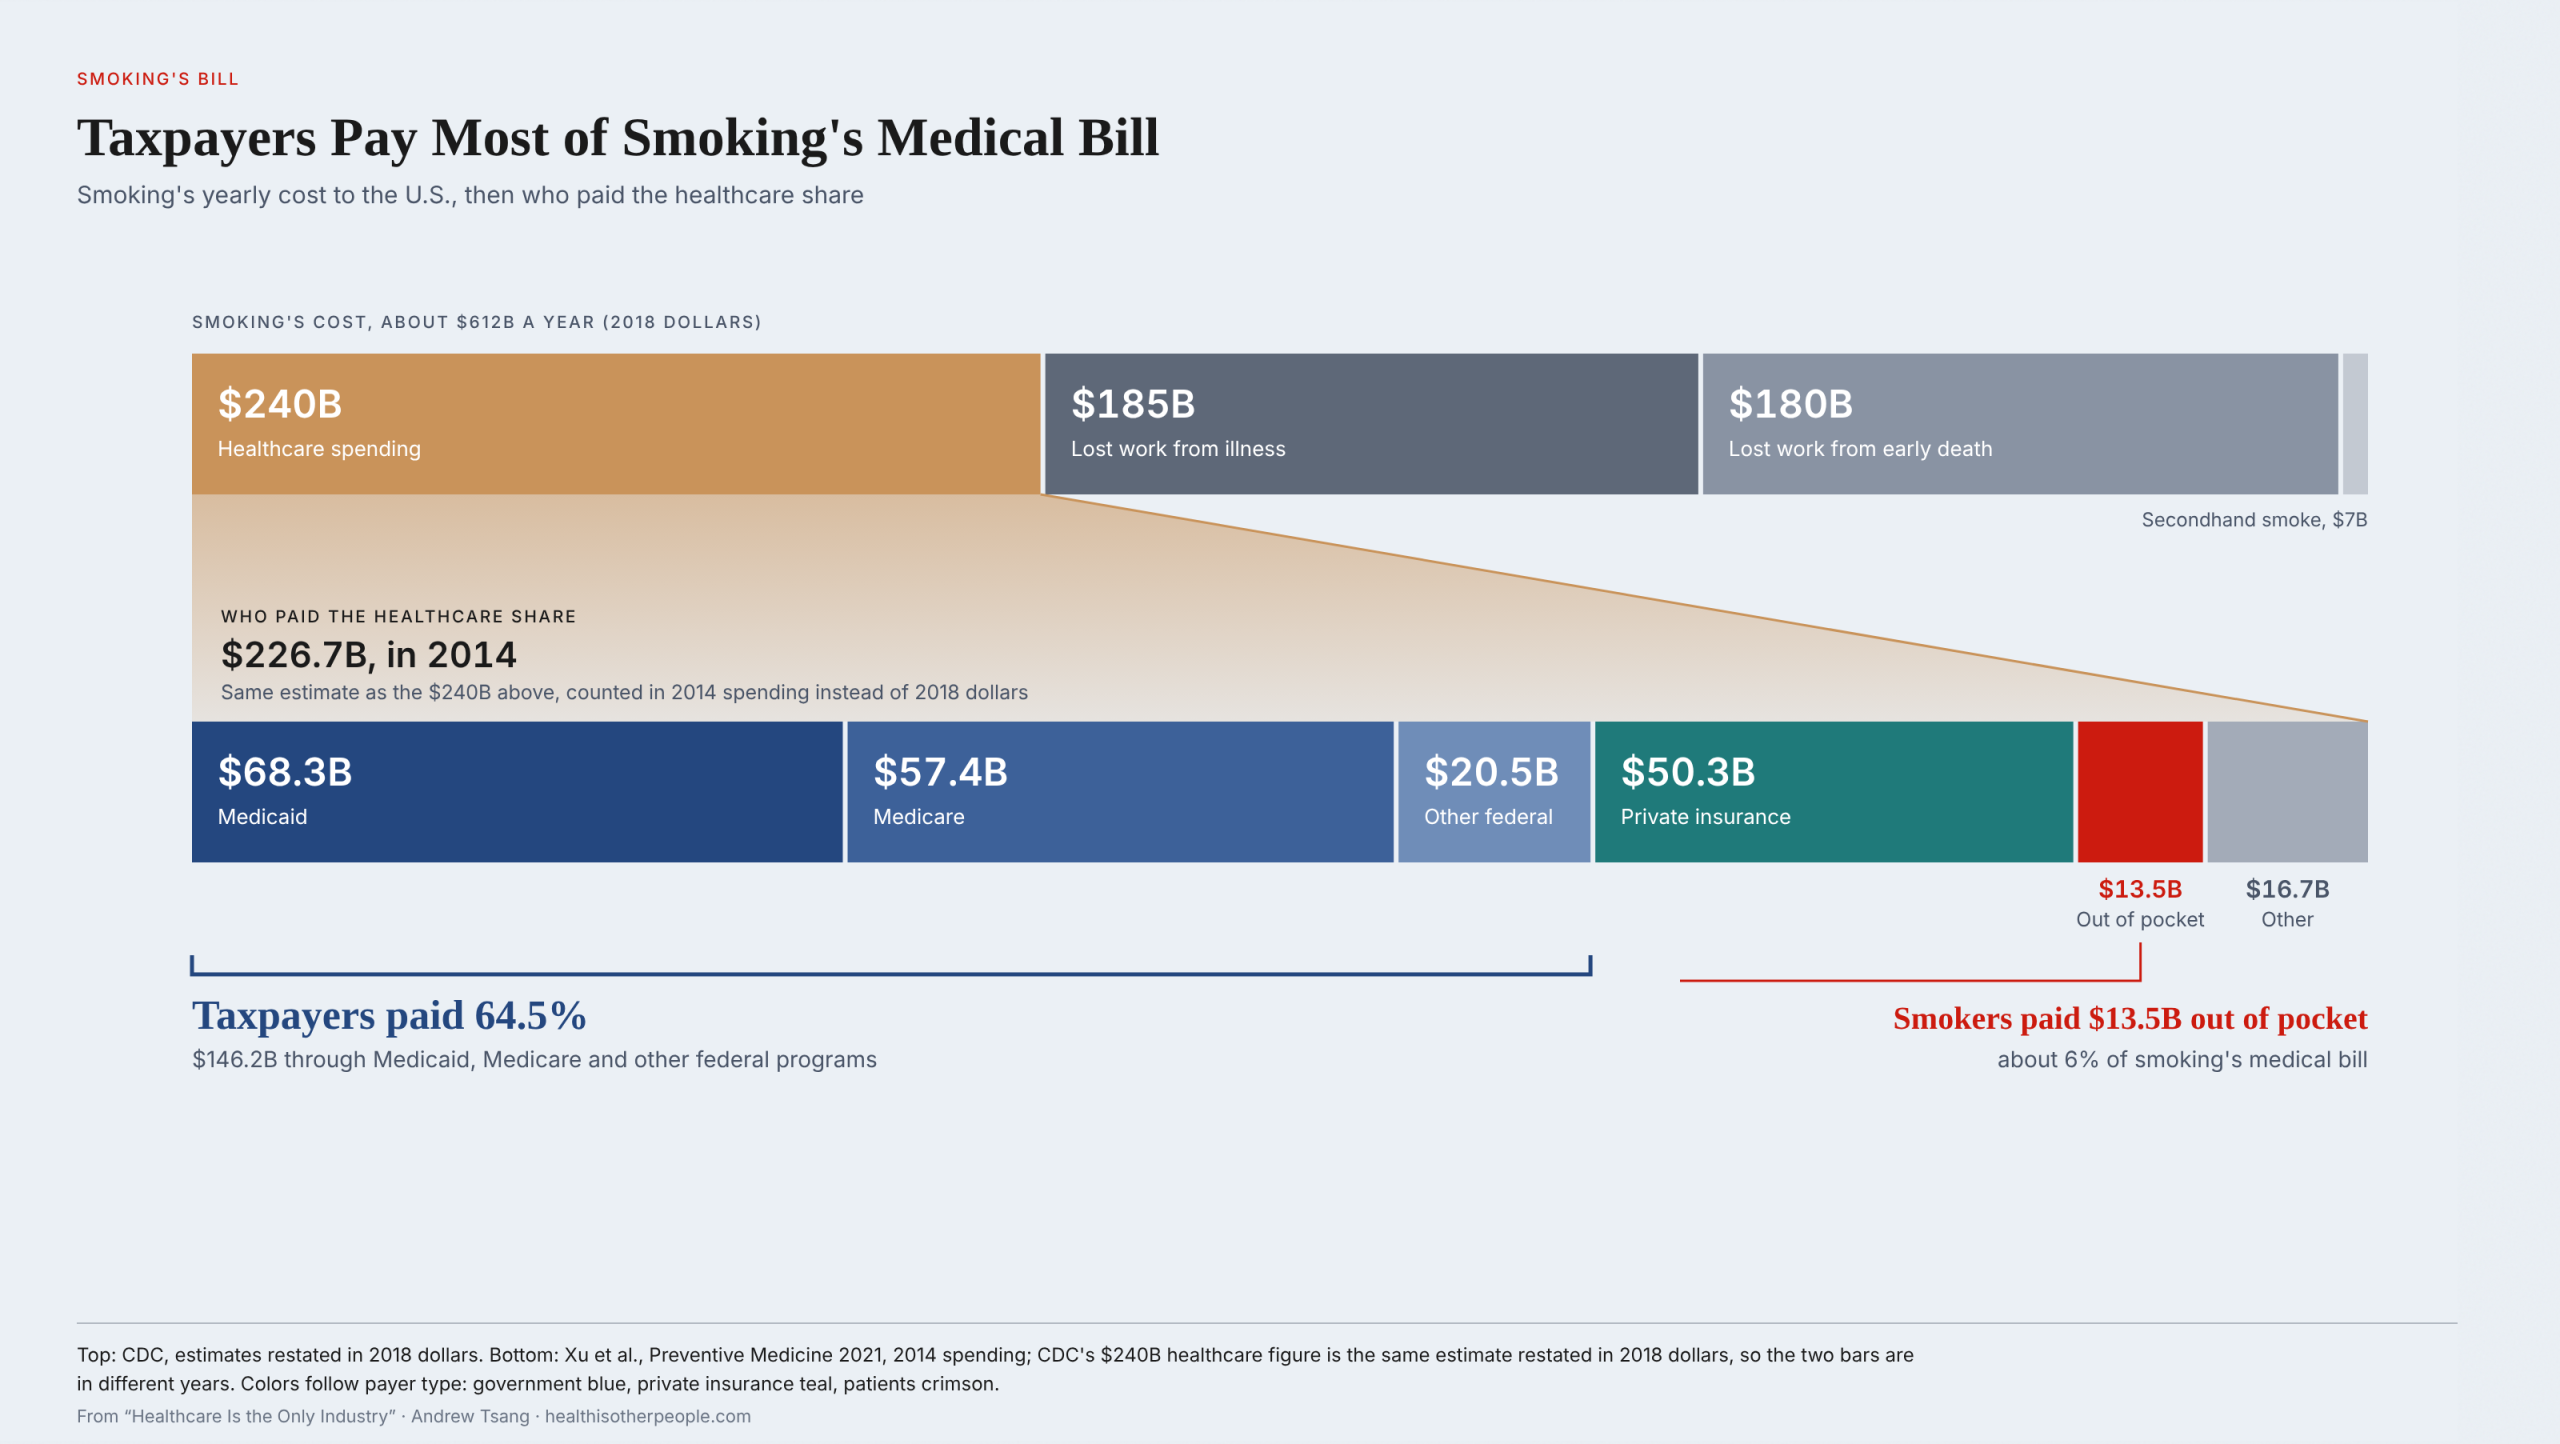
That is the generous side of the accounting, where healthcare produces benefits other industries get to keep. The other side coming in shows that healthcare treats damage other industries get paid to cause. Due to size alone, tobacco use is the best example. A cigarette company books a sale and keeps the profit. The lung disease shows up years later, in a clinic, on an insurer’s claim, in a hospital bed, and the company never sees that bill. Cigarettes are a textbook example of a negative externality, a product whose harm lands on people who were never part of the sale. Smoking generated more than $240 billion in healthcare spending. The bill got big enough that states sued the tobacco companies to claw back the public money spent treating smokers, and a 1998 settlement with forty-six states still has them paying. It took a nationwide legal fight to send even part of smoking’s bill back out of healthcare.

Stacked bars show roughly 612 billion dollars in annual smoking costs in 2018 dollars and a separate 2014 medical-spending breakdown, with taxpayers paying 64.5 percent of the medical bill.
Figure 6. Taxpayers pay most of smoking’s medical bill. Philip Morris sells a pack of smokes, but the taxpayers buy most of the lungs.

Part of what we call healthcare’s cost problem is really the cost of everybody else’s products. The smoker’s cancer treatment still enters the accounts as healthcare spending, where it joins the evidence that healthcare costs too much. Yes – hospitals can overcharge, insurers can overburden, and drugs can be overprescribed. But this patient arrived with a disease a cigarette company was paid to cause! Fixing the billing department won’t undo what put them in the bed.

Continue reading…

Healthcare Is the Only Industry (Part 1)

Andrew Tsang

By ANDREW TSANG

Healthcare only industry in the room for your first breath – and it bills you for it.

The only industry in the room for your last one – and its claim outlives you.

The only industry that hires more humans every year to take care of everybody else.

The only industry whose best work is the sickness you never knew was coming.

The only industry that’s left holding the smoker’s lungs, the drinker’s liver, and the soda kid’s blood sugar – long after everyone else has cashed out.

The only industry that still needs a person at the bedside when the machines do the rest.

The only industry that has nearly a fifth of everything we make, and is still growing.

Healthcare should keep growing. It is the only industry whose whole product is human capacity—more years, and more ability to use them. It is the only industry that takes in the damage every other industry leaves behind. I don’t care how big tech, retail, autos or manufacturing get. Past a point we stop wanting more of what they sell, and none of them gets handed the bill for anyone else’s harm. As their machines take over more of the work, healthcare is where our money, our people, and our ambition should go. It will grow into whatever we pay it to do.

Continue reading…

Science FTW

By KIM BELLARD

Science won. At least, that’s one of the takeaways from last week’s midterm elections. If you were one of the 124 million Americans who voted, you probably already know that there was a Blue Wave, with resounding Democrat victories across the country, even in historically red areas.

Georgia not only reelected its Democrat Senator – no surprise — but also elected a Democrat Governor, who will be the first black woman governor in the country, no less. Iowa elected a Democrat Senator and Governor. South Carolina is sending a Democrat to the Senate, and Mississippi – Mississippi!!! – may as well. Even Kansas elected a Democrat Senator, the first such in almost 100 years. Ohio and Texas not only flipped their Senators and Governors but Democrats won all the statewide elections.

Truly strange times.

I’m allowing myself to hope that we’ll finally have a Congress that will fulfill its constitutional duties of acting as a counterbalance to the power of the Presidency, but one thing I’m particularly excited about is the prospect these results will be less about being a Blue wave than what The Washington Post called a “STEM wave.” Among the newcomers to Congress are a record number of physicians and scientists. They’re going to have their hands full.

Much has been written (including by me) about the Trump Administration’s attacks on science. Just last week The New York Times reported on How Trump Is Dismantling America’s Scientific Research Machine. Amid cuts in research grants, resignations and firings of top scientists, departures of leading scientists to other countries, and reductions in Ph.D. students, the Defense Department warned that its “innovation engine is at risk of stalling.” Even people who aren’t defense hawks should realize that spells big trouble for American science in general, and for all of us.

A year ago I wrote about how organizations like 314 Action and Stand Up for Science were leading the resistance to the attacks on science. 314 Action, for example, spent some $23 million on pro-science candidates, doubling its 2024 donations. Shaughnessy Naughton, president of 314 Action, told Alexander Nazaryan of The New York Times that the election results, especially the incoming scientist lawmakers, represent “a real repudiation of what has been two terrible years for science and public health.”

Continue reading…

Amy Bucher, Lirio Health

Lirio Health is an interesting under-the-radar company, which works with plans, providers and others to try to influence the behavior of their members and patients. Of course, everybody wants to change the behavior of human beings, and it’s been proven over the years to be very hard. Lirio probably has more PhDs per square foot than any other company in this sector. I spoke with one of them, the Chief Behavior Officer, Amy Bucher, and she showed me a wide variety of case studies in which they are using a wording approach and psychographics to nudge people to better behaviors. A great discussion on how and whether we can use psychology to improve health.–Matthew Holt

The transcript (made by Youtube and Claude so blame AI for any mistakes!)

Continue reading…