Categories

Above the Fold

THCB 20th Birthday Classic: Value-based care – no progress since 1997?

As the 20th Birthday rolls on I thought I’d bring out a more recent piece first published in October 2020, albeit one that relies heavily on 25 year old data to make a point. This is some evidence to back up Jeff Goldsmith’s comment on the original that for all the talk “ ‘Value based” payment is a religious movement, not a business trend’ ” By the way, Humana updated these numbers last year and there’s been basically no change — Matthew Holt

By MATTHEW HOLT

Humana is out with a report saying that its Medicare Advantage members who are covered by value-based care (VBC) arrangements do better and cost less than either their Medicare Advantage members who aren’t or people in regular Medicare FFS. To us wonks this is motherhood, apple pie, etc, particularly as proportionately Humana is the insurer that relies the most on Medicare Advantage for its business and has one of the larger publicity machines behind its innovation group. Not to mention Humana has decent slugs of ownership of at-home doctors group Heal and the now publicly-traded capitated medical group Oak Street Health.

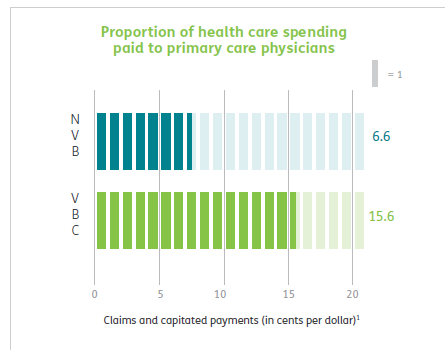
Humana has 4m Medicare advantage members with ~2/3rds of those in value-based care arrangements. The report has lots of data about how Humana makes everything better for those Medicare Advantage members and how VBC shows slightly better outcomes at a lower cost. But that wasn’t really what caught my eye. What did was their chart about how they pay their physicians/medical group

What it says on the surface is that of their Medicare Advantage members, 67% are in VBC arrangements. But that covers a wide range of different payment schemes. The 67% VBC schemes include:

  • Global capitation for everything 19%
  • Global cap for everything but not drugs 5%
  • FFS + care coordination payment + some shared savings 7%
  • FFS + some share savings 36%
  • FFS + some bonus 19%
  • FFS only 14%

What Humana doesn’t say is how much risk the middle group is at. Those are the 7% of PCP groups being paid “FFS + care coordination payment + some shared savings” and the 36% getting “FFS + some share savings.” My guess is not much. So they could have been put in the non-VBC group. But the interesting thing is the results.

Continue reading…

The Next Pandemic May Be an AI one

By KIM BELLARD

Since the early days of the pandemic, conspiracy theorists have charged that COVID was a manufactured bioweapon, either deliberately leaked or the result of an inadvertent lab leak. There’s been no evidence to support these speculations, but, alas, that is not to say that such bioweapons aren’t truly an existential threat.  And artificial intelligence (AI) may make the threat even worse.

Last week the Department of Defense issued its first ever Biodefense Posture Review.  It “recognizes that expanding biological threats, enabled by advances in life sciences and biotechnology, are among the many growing threats to national security that the U.S. military must address.  It goes on to note: “it is a vital interest of the United States to manage the risk of biological incidents, whether naturally occurring, accidental, or deliberate.”  

“We face an unprecedented number of complex biological threats,” said Deborah Rosenblum, Assistant Secretary of Defense for Nuclear, Chemical, and Biological Defense Programs. “This review outlines significant reforms and lays the foundation for a resilient total force that deters the use of bioweapons, rapidly responds to natural outbreaks, and minimizes the global risk of laboratory accidents.”

And you were worried we had to depend on the CDC and the NIH, especially now that Dr. Fauci is gone.  Never fear: the DoD is on the case.  

A key recommendation is establishment of – big surprise – a new coordinating body, the Biodefense Council. “The Biodefense Posture Review and the Biodefense Council will further enable the Department to deter biological weapons threats and, if needed, to operate in contaminated environments,” said John Plumb, Assistant Secretary of Defense for Space Policy. He adds, “As biological threats become more common and more consequential, the BPR’s reforms will advance our efforts not only to support the Joint Force, but also to strengthen collaboration with allies and partners.”

Which is scarier: that DoD is planning to operate in “contaminated environments,” or that it expects these threats will become “more common and more consequential.” Welcome to the 21st century.  

Continue reading…

Torben Nielsen, CEO, Uptiv Health

Early this month I caught up with Torben Nielsen who is now CEO of Uptiv Health. Another one from the Redesign Health factory, Uptiv Health came out of stealth recently with the goal of improving the experience and reducing the cost of those patients who have to have regular infusion treatments. Uptiv Health just raised $7.5m and is opening its first location in Detroit at the end of August 2023, with a goal of becoming the health home of those chronic disease patients. Why do we need a new offering in infusion care? Torben will tell you–Matthew Holt

Lash of St. Francis

BY MIKE MAGEE

On September 25, 1939, Southern California woke with fear of The Lash of St. Francis or El Cordonazo on the horizon. The term refers to northwestern tracking, cyclone-laden storms that can hit the western shores of Mexico and California most commonly around the Feast of Saint Francis, on October 4th. This one made landfall at San Pedro, California.

The calamity that day in Southern California was a rare event, the only one of its kind in the 20th century. The last one to hit, prior to this was in San Diego on October 2,1858. The Earth’s rotation normally assures that such cyclones in this region move from east to west, and out to sea. But the 1939 storm was the exception, and the big problem was the rain, some 5 1/2 inches over a 24-hour period (though the town of Indio, in the Coachella Valley of Southern California’s Colorado Desert region experienced 7 inches and buried the valley in 4 feet of water. Forty-five died on land, and 48 perished at sea. One positive – the storm marked the end of a 1-week heat wave where Los Angeles reached 107 F degrees and claimed 100 lives.

History repeated itself 84 years later this weekend, with a memorable “Lash” on the backend of a summer heat wave. The human, economic, and ecological tolls remain to be calculated. But one thing is for certain, global warming has arrived, and with it the production of both heat and water and a new, all too familiar meteorological phenomenon, the “atmospheric river.”

NOAA defines “atmospheric river” this way: “Atmospheric rivers are relatively long, narrow regions in the atmosphere – like rivers in the sky – that transport most of the water vapor outside of the tropics. While atmospheric rivers can vary greatly in size and strength, the average atmospheric river carries an amount of water vapor roughly equivalent to the average flow of water at the mouth of the Mississippi River. Exceptionally strong atmospheric rivers can transport up to 15 times that amount. When the atmospheric rivers make landfall, they often release this water vapor in the form of rain or snow.”

To be clear, these drenching above-ground collections of water are generally a blessing because they provide most of the much-needed precipitation to California’s dry areas and replenish the water cycles in the region. But as the Earth has warmed, they more frequently represent “too much of a good thing”, and are now responsible for 90% of California’s flood damage.

Continue reading…

THCB 20th Birthday classics: A Brief History of Price Controls by Annoyed Republican Administrations

By UWE REINHARDT

One of the greatest pleasures of running THCB has been to get to know and host the writings of some of my health policy heroes. This week I have already published work from Jeff Goldsmith, and Ian Morrison & Michael Millenson among others will be featured next week (as the party won’t quite stop). Perhaps one of the most amazing things was that the doyen of health economists, Uwe Reinhardt, offered to write some original pieces for THCB…prodded by former editor John Irvine. This is one of my favorites, riffing on a talk I heard him give in (I think) 1993 about how HCFA was like the Kremlin and how free market Reaganite Republicans had made it so. This piece is from Jan 2017 and Uwe sadly died that November.–Matthew Holt

Although, unlike most other nations, the U.S. has only two parties worth the name, their professed doctrines compared with their actions strikes me as more confusing than the well-known Slutsky Decomposition which, as everyone knows, can be derived simply from a straightforward application of Kramer’s rule to a matrix of second partial derivatives of a multivariable demand function.

The leaders of the drug industry, for example, probably are now breaking out the champagne in the soothing belief that their aggressive pricing policies for even old drugs are safe for at least the next eight years from the allegedly fearsome, regulation-prone, price-controlling Democrats. My advice to them is: Cool it! Follow me through a brief history of Republican health policy, to learn what Republicans will do to the health-care sector when it ticks them off.

Republicans like to tar Democrats over allegedly socialist policy instruments such as price controls, global budgets and deficit-financed government spending. Democrats usually roll over to take that abuse, almost like hanging onto their posteriors signs that says “Kick me.”  I say “abuse,” because Republicans have never shied away from using the Democrats’ allegedly left-wing tactics when health care chews up their budgets or turns voters against them.

Continue reading…

Academics Weigh In On How To Bring Down Trump

By MIKE MAGEE

This week, as a fourth indictment came due, a tragic Donald Trump headed back to social media, digging himself into a hole that will eventually lead to some personal hell. But before Donald Trump, there was William Frederick Kohler.

He made his appearance on the American stage on February 28, 1995, an historian who had just completed his “Great Work” – The Guilt and Innocence of Hitler’s Germany. He was odd and dark and duplicitous. His life’s work was ready to go. All that was left was to write the introduction to his book. Instead his attention was diverted, as he followed his impulse to memorialize his own story dedicated to the “concealment of history beneath my exposition of it.”

Secretive and opaque, he was focused on a very special audience he labeled the “Party of the Disappointed People”, a group with whom he shared the affinity “that the loss has been caused in great part by others.” He hid the pages of the new and very personal (but incomplete) story from wife Marta inside the pages of the near completed Nazi history. And for some reason, he inexplicably headed to his basement and began to dig a tunnel to escape (or uncover) evil.

Kohler, like Trump, was not normal. Those who have analyzed his character describe him this way:  “Preoccupied with evil, the nature of truth, and the effects of an individual’s relationship with others, he recalls his bookish childhood with a mother who drank to remember the ‘good old days’ and a bigoted father; graduate work in prewar Germany, where he hurled a brick on Kristallnacht; his unhappy marriage; and the lost love of his life, Lou, a former student. Kohler’s story exhibits the same inconsistencies and deceits he finds in history: Kohler, the personal memoirist … is as unreliable as Kohler, the eminent historian. A virtuoso performance without a grand finale.”

Kohler is the fictional creation of philosopher and novelist William H. Gass, author of the award winning novel, “The Tunnel.”  The author is described in the opening line of his 2017 New York Times obituary as “a proudly postmodern author who valued form and language more than literary conventions like plot and character.” He died on December 7 of that year, at age 93, in St. Louis, where he had taught philosophy and linguistics for 30 years. Born in Fargo, North Dakota, he was translocated to Warren, Ohio at 6 months, and raised according to his own account by “an abusive, racist father and a passive, alcoholic mother.” These revealing personal details trace back to a writing style he developed and labeled, “metafiction,” or stories in which the author inserts himself.

Of more relevance to America’s current political dilemma is that Gass received his PhD from Cornell in 1954, in return for his dissertation “A Philosophical Investigation of Metaphor.” A metaphor, as we know, is “a figure of speech in which a word or phrase literally denoting one kind of object or idea is used in place of another to suggest a likeness or analogy between them (as in drowning in money).”

Gass’s love of metaphor is on full display in “The Tunnel”.  You can almost hear the beloved high school advanced placement English teacher pleadingly asking her sleepy students “What do you think the tunnel represents?” Of the novel, one critic wrote, “As the novel progresses we see the lies, half-truths, violent emotions, and relative chaos of Kohler’s life laid bare, and while he continues to dig away at the memories of his past he also begins digging a tunnel out from the basement where he works, a reflection of his tunneling through himself.”

Beyond Gass’s own story line, and that of William Frederick Kohler, one can easily catch glimpses of  Donald Trump.  As he entered the strange world of politics, he embraced the use of metaphor with memorable 3 and 4 world phrases like “drain the swamp”, “the system is rigged,” and “take our country back.”

Continue reading…

THCB Gang Episode 133, Thursday August 17

Joining Matthew Holt (@boltyboy) on #THCBGang on Thursday August 17 at 1pm PST 4pm EST are futurist Jeff Goldsmith: medical historian Mike Magee (@drmikemagee); policy expert consultant/author Rosemarie Day (@Rosemarie_Day1); and patient safety expert and all around wit Michael Millenson (@mlmillenson);

You can see the video below & if you’d rather listen than watch, the audio is preserved as a weekly podcast available on our iTunes & Spotify channels.

THCB 20th Birthday Classic: As I’ve always suspected, Health Care = Communism + Frappuccinos

By MATTHEW HOLT

Our 20th birthday continues with a few classics coming out. Back in 2005 I was really cutting a lyrical rug, and would never miss a chance to get that Cambridge training in Marxism into use. This essay about whether health care should be a public or private good has always been one of my favorites, even if I’m not sure Starbucks is still making Frappuccinos. And 18 years later the basic point of this essay remains true, even if many of you will not have a clue who Vioxx or Haliburton were or why they mattered back then!

Those of you who think I’m an unreconstructed commie will correctly suspect that I’ve always discussed Marxism in my health care talks. You’d be amazed at how many audiences of hospital administrators in the mid-west know nothing about the integral essentials of Marx’s theory of history. And I really enjoy bring the light to them, especially when I manage to reference Mongolia 1919, managed care and Communism in the same bullet point.

While I’ve always been very proud of that one (err.. maybe you have to be there, but you could always hire me to come tell it!), even if I am jesting, there’s a really loose use of the concept of Marxism in this 2005 piece (reprinted in 2009) called A Prescription for Marxism in Foreign Policy from (apparently) libertarian-leaning Harvard professor Kenneth Rogoff. He opens with this little nugget:

“Karl Marx may have suffered a second death at the end of the last century, but look for a spirited comeback in this one. The next great battle between socialism and capitalism will be waged over human health and life expectancy. As rich countries grow richer, and as healthcare technology continues to improve, people will spend ever growing shares of their income on living longer and healthier lives.”

Actually he’s right that there will be a backlash against the (allegedly) market-based capitalism — which has actually been closer to all-out mercantilist booty capitalism — that we’re seen over the last couple of decades. History tends to be reactive and societies go through long periods of reaction to what’s been seen before. In fact the 1980-20?? (10-15?) period of “conservatism” is a reaction to the 1930-1980 period of social corporatism seen in most of the western world. And any period in which the inequality of wealth and income in one society continues to grow at the current rate will eventually invite a reaction–you can ask Louis XVI of France about that.

But when Rogoff is talking about Marxism in health care what he really means is that, because health care by definition will consume more and more of our societal resources, the arguments about the creation and distribution of health care products and services will look more like the arguments seen in the debates about how the government used to allocate resources for “guns versus butter” in the 1950s. These days we are supposed to believe that government blindly accepts letting “the market” rule, even if for vast sways of the economy the government clearly rules the market, which in turn means that those corporations with political influence set the rules and the budgets (quick now, it begins with an H…).

Continue reading…

What Robotaxis Mean for Healthcare

BY KIM BELLARD

You may have seen that last week the California Public Utilities Commission (CPUC) gave approval for two companies to operate self-driving taxicabs (“robotaxis”) in San Francisco, available 24/7 and able to charge fares.  Think Uber or Lyft but without drivers. 

It has seemed inevitable for several years now, yet we’re not really ready.  It reminds me, of course, of how the future is coming fast for healthcare too, especially around artificial intelligence, and we’re not really ready for that either.

The two companies, Cruise (owned by GM) and Waymo (owned by Alphabet) have been testing the service for some time, under certain restrictions, and this approval loosens (but does not completely remove) the restrictions. The approval was not without controversy; indeed, the San Francisco police and fire departments,  among others, opposed it. “They are failing to regulate a dangerous, nascent industry,” said Justin Kloczko, a tech and privacy advocate for consumer protection non-profit Consumer Watchdog.  

The companies brag about their record of no fatalities, but the San Francisco Municipal Transportation Agency has collected almost 600 “incidents” involving autonomous vehicles, even with what they believe is very incomplete reporting.  “While we do not yet have the data to judge AVs against the standard human drivers are setting,” CPUC Commissioner John Reynolds admitted, “I do believe in the potential of this technology to increase safety on the roadway.”

I’m willing to stipulate that autonomous vehicle technology is not quite there yet, especially when mostly surrounded by human-driven vehicles, but I also have great confidence that we’ll get there quickly, and that it will radically change not just our driving but also our desire for owning vehicles. 

One of the most thoughtful discussions I’ve on the topic is from David Zipper in The Atlantic. He posits: 

A century ago, the U.S. began rearranging its cities to accommodate the most futuristic vehicles of the era, privately owned automobiles—making decisions that have undermined urban life ever since. Robotaxis could prove equally transformative, which makes proceeding with caution all the more necessary.

Continue reading…

THCB 20th Birthday Classic: McKinsey wants to inspire lots of change; caveat emptor

by MATTHEW HOLT

So to celebrate 20 years, we’ll be publishing a few classics for the next week or so. This is one of my faves from the early days of THCB, back in 2006. It’s interesting to compare it with Jeff Goldsmith’s NEW piece from yesterday on vertical integration because at the time a pair of Harvard professors, Michael Porter and Elizabeth Teisberg were telling hospitals to change their operations in a way that seemed to me were going to destroy their business–cut down to one or two service lines they were best at and stop with the rest. McKinsey picked up on this and I went to town on why they were all wrong. In fact in the next decade and a half, despite all the fuss and consulting fees generated, almost no hospital system did anything other than merge horizontally with local competitors, stick up its prices, and buy feeder systems of primary care doctors or ally with/bribe specialists to keep their procedural referrals up. The result is the huge regional oligopolies that we have now. Despite all the ignoring of their advice, I don’t think Porter/Teisberg or McKinsey went broke in that same period.–Matthew Holt

McKinsey, an organization that prides itself on increasing the amount of consulting dollars it gets paid by improving the strategic direction of American business is making another foray into health care.

You may recall their last study on CDHPs was roundly criticized (see Tom Hillard for a good example including a hilarious and brutal smackdown of their research methodology in the last couple of paras), and this time they cleverly aren’t bothering with data—in fact they’re basically copying Porter and Teisberg. The piece, by Kurt Grote, Edward Levine and Paul Mango, is about hospitals and how they need to get into the 21st century.

And of course the idea is that hospitals need to change their business approach.  Well, given that I hadn’t noticed a rash of hospital closings and the the industry as a whole has been growing its revenues pretty successfully over the years, what exactly are the problems?

The rise of employer-sponsored insurance in the 1930s and 1940s, and the emergence of government-sponsored insurance in the 1960s all insulated hospitals from the need to compete for patients. Today hospitals are “price takers” for nearly 50 percent of their revenues, which is subject to the political whims of the federal and state governments. Hospitals are also required to see, evaluate, and treat virtually any patient who shows up, solvent or not. Furthermore, physicians were productive because hospitals put a great deal of capital at their disposal. Yet these hospitals didn’t enforce standardized and efficient approaches to the delivery of care. At many hospitals today, doctors still bear only limited economic
responsibility for the care decisions they make. Little wonder that it is often they who introduce expensive—and sometimes excessive—nonreimbursable technologies or that hospitals not only suffer from declining margins but are also performing less well than other players in the health care value chain
 

The piece then has a pretty incomprehensible chart that compares the EBITDA (profit) of hospitals compared to drug companies and insurers. Surprisingly enough they make a whole lot less EBITDA than those businesses–although long time THCB readers will know we’ve been well down that path. And apparently their margins got worse and then better (from 25% in 1990 to 15% in 1995 to 10% in 2000 but back up to 15% in 2004).

McKinsey’s answer, basically filched from Porter/Teisberg, is for hospitals to specialize in particular service lines, stop being generalists and start trying to please the consumer who’ll be choosing among them. As a general mantra, this might be good for consultants to stick up on Powerpoint, but to be nice it’s massively oversimplified, and to be nasty it’s just plain wrong for most hospitals for the current and foreseeable medium-term future.

Their analysis ignores the fact that there are (at least) three broad categories of hospitals–inner city and rural  safety-net providers, big academic medical centers, and suburban community hospitals. Each of these has a completely different audience, completely different set of incentives, and more to McKinsey’s point, different profit margins.

Right up front they talk about the 50% of revenue that comes from the government–but for the first two categories, it’s more than that! And for everyone, as public programs grow, it’s going to be increasing.

Those hospitals relying on Medicare make most of their money but playing very careful attention to the DRG mix. The ones who play that game well and make most profit on Medicare outliers (like the for-profits McKinsey features in its metrics) don’t really want to change that by stopping their patients becoming those outliers, because if they get better at treating patients, they make less money. Brent James’ famous Intermountain story tells the truth, and until Medicare really changes the way it pays, you don’t want to be ahead of that curve. Intermountain may have spent more than 10 years leaving money on the table, but those rich Mormons can afford it.

Meanwhile, for the mainstream community hospitals, as more and more services and patients leave the building, the imperative is not to change their business model, it’s to get their hands on that revenue that’s leaving with them. That’s why most big hospitals are now-co-investing with physicians in specialty hospitals et al. But while that’s a defensive battle to build better “hotels” for the star surgeons, it’s still about building better “hotels”–not junking the model of being the nicest possible host to the big time admitting surgeons.

The McKinsey/Porter/Teisberg theory is of course that if you get good at one service line, you’ll be attractive to consumers, and that they’ll choose you. There is more truth to this notion now than there was five years ago, but not much more. Doctors choose hospitals for their patients. That’s always been the case, other for those that get admitted via the ED, and that’s a function of location. That’s why hospitals suck up to surgeons. But even when consumers make choices, they’re not very active consumers beyond the deductible, and basically all hospital spending is beyond the deductible, and even in the cash non-hospital business (the stuff like genetic testing) most consumers take their doctor’s advice.

Which leads of course to who the other real consumer for the hospital is, and that’s the third party payer. First rule of dealing with payers is to figure out how to play the Medicare system well enough that you make it very profitable, but not too “well” that you get busted, a la Columbia/HCA, Tenet & St Barnabas.

Second rule is that you need to get bargaining strength against the health plans. No one can pretend that health plans really care in a global sense about having their providers cut costs and improve care delivery. They may say they care about it, but health plans add a chunk on the top of what they pay providers and stick that to their clients (usually employers) — who basically take it in a mealy mouthed way.

There is, though, a fight in any local market about where to draw the line on hospital pricing. But this fight is not about having providers from outside (or even within) the region swooping in to capture all a payer’s business with better pricing on certain service lines, and payers moving patients to these disease-specific treatment centers.  Well, it is about that in the McKinsey/Porter/Teisberg fantasy land, but in reality the fight is about setting global pricing for all the services a payer needs for its members in that region.

Continue reading…