Episode 54 of “The THCB Gang” was held on Thursday, May 13. Matthew Holt (@boltyboy) was joined by regulars: policy expert consultant/author Rosemarie Day (@Rosemarie_Day1); medical historian Mike Magee (@drmikemagee), THCB regular writer Kim Bellard (@kimbbellard) employer health expert Jennifer Benz (@jenbenz); and WTF Health host & Health IT girl Jessica DaMassa (@jessdamassa).
The topic ended up looking at the role of employers in dealing with inequality in health care, and whether the digitally enabled primary care navigation organizations could help. A great discussion!
Then video is below. If you’d rather listen, the audio is preserved as a weekly podcast available on our iTunes & Spotify channels.
Last year was a remarkable time for digital health. Obviously it was pretty unusual and tragic for the world in general as the COVID-19 pandemic continued to wreak havoc. We mourn those lost, and we praise our front line health workers and scientists. But for digital health companies, in almost no time 2020 changed from fear of a market collapse to what became a massive funding boom.
But no-one has reported from the ground what this means for digital health companies, of which there are perhaps 10-15,000 worldwide with maybe 6-8,000 based in the United States. Despite the headlines, most are not pulling down $200m funding rounds or SPACing out. So working with professional services firm Wipfli, we at Catalyst @ Health 2.0 decided to find out what digital health companies experienced in this most extraordinary year.
Between Thanksgiving 2020 and mid-March 2021, we surveyed more than 300 members of the digital health ecosystem, focusing on leaders from more than 180 private (and a few public) digital health companies. We asked them about their market, their experience during COVID-19, and what they thought of the environment. We also asked them about the mechanics of running their businesses. The results are pretty interesting.
The Key Message: COVID-19 was very good for digital health companies–on average. Most are very optimistic but, despite the massive increase in funding since the brief (but real) post-lockdown crash, most digital health companies remain small and struggling for funding, revenue, and customers.
We also heard from investors, and a bigger group we called “users” (mostly payers, providers, pharma, non-healthcare tech companies, e-patients & consultants). While these “users” also saw a big trend towards the use of (and, to a lesser extent, paying for) digital health tools and services, they were not as gung-ho as were digital health companies or investors, who were even more optimistic.
The summary deck containing the key findings is below and there is more analysis and commentary below the jump.
Episode 53 of “The THCB Gang” was live-streamed on Thursday, May 5 at 1pm PT -4PM ET. Matthew Holt (@boltyboy) was joined by regulars: futurists Ian Morrison (@seccurve) & Jeff Goldsmith; privacy expert and now entrepreneur Deven McGraw @HealthPrivacy; policy expert consultant/author Rosemarie Day (@Rosemarie_Day1); medical historian Mike Magee (@drmikemagee), & THCB regular writer Kim Bellard (@kimbbellard)
Matthew was celebrating Chelsea’s Champion’s League Semi final win, but the rest of the gang talked about some big picture issues behind public health, COVIUD and health care policy!
The video is below but if you’d rather listen to the podcast. it will be available on our iTunes & Spotify channels from Friday.
Thursday’s #THCBGang was another with a special guest. Matthew Holt (@boltyboy) was joined by regulars, employer health expert Jennifer Benz (@jenbenz); patient safety expert and all around wit Michael Millenson (@MLMillenson); WTF Health host & Health IT girl Jessica DaMassa (@jessdamassa); & Consumer advocate & CTO of Carium Health, Lygeia Ricciardi (@Lygeia).
Our special guest was Shantanu Nundy @DrNundy who is Chief Medical Officer of Accolade and more importantly author of new book Care After Covid. We dug into the question about what the post-covid health care system will look like, while I let slip why I’m grumpy Accolade just paid $450m for Plushcare! (You have to wait for the very end for that!)
Then video is up below. If you’d rather listen, the audio is preserved as a weekly podcast available on our iTunes & Spotify channels.
Episode 51 of “The THCB Gang” was live-streamed on Thursday, Jan 21. You can see it below! Matthew Holt (@boltyboy) was joined by regulars: futurists Ian Morrison (@seccurve) & Jeff Goldsmith; privacy expert and now entrepreneur Deven McGraw @HealthPrivacy; and digital health guru Fard Johnmar (@fardj). We really dug into vaccines, vaccine passports and what they means for the future of health and society. Great conversation, benefitting a lot from having a fabulous lawyer on the show!
If you’d rather listen to the episode, the audio is preserved from Friday as a weekly podcast available on our iTunes & Spotify channels.
Quick now: what’s the biggest single component of President Biden’s infrastructure plan (a.k.a The American Jobs Plan)? Fixing roads and bridges? Upgrading the power grid? Preparing the nation for electric vehicles? Giving all Americans access to broadband? Wrong. If you guessed home and community services, you’ve been paying attention.
President Biden is proposing $400b (out of some $2 trillion total spending) for this component, compared to, for example, $115b for roads and bridges or $174b to support electric vehicles. He wants to improve the pay of home care workers, fund more of those jobs, and ensure more people have access to home and community services.
All laudable goals, but not nearly enough, and not spent on the right things. I worry that we may miss a generational opportunity to fundamentally rethink the infrastructure for long-term care.
Opponents of the Biden plan argue that this part of the program is not “infrastructure” in any normal use of the word, and cynics believe it is more about satisfying the SEIU. On the other hand, long-term care advocates worry that it doesn’t do anything to improve nursing homes, nor the existing long-term care financing mechanisms.
No one is happy with our long-term care system, except maybe the people profiting from it. We spend well over $300b annually on long-term care services, plus billons more in unpaid care, but that doesn’t seem to be money well spent. Long-term care makes the rest of our messed-up healthcare system look futuristic. Since 70% of us are likely to require some kind of long-term care assistance during our lifetime, this is an issue we should all care about.
Well the half-century is up for #THCBGang and it’s been a lot of fun bantering with some of the cognoscenti of health tech, business & policy over most of the last year.
There was a little discussion of Robert’s new book Uncaring (although there’ll be more about that on THCB later) and a lot of discussion about his experience at Kaiser Permanente, what went right, what went wrong and why it never traveled nationwide–and what that all means for a new generation of medical groups. And we didn’t forget the vaccine rollout, and even whether it was safe to be on a plane!
You can see the video below live and the audio will be on our podcast channel (Apple/Spotify) from Friday — Matthew Holt
A couple years ago I wrote about how healthcare should take customer experience guru Dan Gingiss’s advice: do simple better. Now new research illustrates why this is so hard: when it comes to trying to make improvements, people would rather add than subtract.
That, in a nutshell, may help explain why our healthcare system is such a mess.
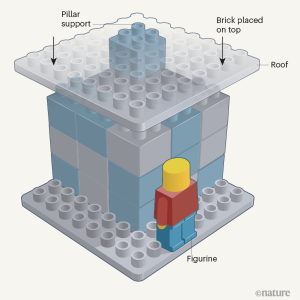
The research, from University of Virginia researchers, made the cover of last week’s Nature, under the catchy title Less Is More. Subjects were given several opportunities to suggest changes to something, such as a Lego set-up, a geometric design, an essay or even a travel itinerary. The authors found: “Here we show that people systematically default to searching for additive transformations, and consequently overlook subtractive transformations.”
In the Lego picture here, for example, when asked how to strengthen the upper platform, most people wanted to add new columns, instead of simply removing the existing column. The researchers note: “The subtractive solution is more efficient, but you only notice it if you don’t jump to an additive conclusion.”
Giving cognitive nudges – like explicitly mentioning the option of deleting something – improved the likelihood that people would come up with subtractive options, but increasing cognitive load (through additional tasks) decreased it. Co-author Benjamin Converse said:
Last year I was heading to a meeting on a Fortune 500 business campus and stumbled upon a bake sale. It was odd to see someone selling cupcakes and breads on the grounds of a major corporation, so I inquired. As it turns out, Judy, an employee, was selling baked goods to finance her insurance deductible for spinal fusion surgery.
“Is this what our system has come to?” I asked myself, “Fundraisers for fusions?” If so, our health system is broken.
No matter how you slice it, Americans spend more on healthcare than any other advanced economy, with households responsible for 28% of that spend according to CMS. The Affordable Care Act (ACA) attempted to address long-standing deficiencies inherent in our fractured healthcare system. However, creating an insurance marketplace hasn’t solved the problem of affordability or the reality of limited access to quality providers. The concept is great, but without private sector buy-in it will never succeed.
President Biden is taking long-overdue steps to address some of the ACA’s shortcomings with Executive Orders. During his campaign, he suggested other actions, like capping marketplace premiums at 8.5% for all income levels with the goal of spurring enrollment and strengthening the ACA with an affordable public option. The recently passed $1.9 trillion stimulus package also incorporates an increase in government subsidies to health insurers for covering workers laid off due to COVID-19 and those purchasing their own coverage.
This is a start. But it’s not enough. We can’t afford to waste time waiting for policymakers to negotiate rules that may be overturned when a party majority flips.
By the time you read this, Microsoft may have already struck a deal with the messaging service Discord. VentureBeatreported two weeks ago that Discord was in an “exclusive acquisition discussion” with an interested party, for a deal that could reach at least $10b. Bloomberg and The Wall Street Journal each quickly revealed that the interested party was Microsoft (and also confirmed the likely price).
Me, I’m wishing that a healthcare company – hey, TelaDoc and UnitedHealth Group, I’m looking at you! – was in the mix.
Let’s back up. If you are not a gamer, you may not know about Discord. It was launched in 2015, primarily as a community for gamers. Originally it focused on texting/chat, but has widened its capabilities to include audio and video. The Vergedescribed it: “Discord is a great mix of Slack messaging and Zoom video, combined together with a unique ability to just drop into audio calls freely.”
Zoom meets Slack meets Clubhouse.
As you might infer from the potential asking price, Discord has done quite well. It has over 140 million monthly users, and, despite having no advertising and offering a free service, generated $130 million in revenues last year (through its “enhanced Discord experience” subscription service Nitro). OK, it still isn’t profitable, but a December funding round gave it a $7b valuation.